Procedures
Tibial Tubercle Osteotomy (Kneecap Realignment) in Doha
Quick answer
Tibial tubercle osteotomy moves the bony bump below the knee, where the patellar tendon attaches, to change how the kneecap tracks. It is used for recurrent kneecap dislocation with abnormal alignment and for selected kneecap cartilage wear, often alongside MPFL reconstruction, says Doha knee surgeon Dr. Pablo Gelber at Aman Hospital.
What is a tibial tubercle osteotomy?
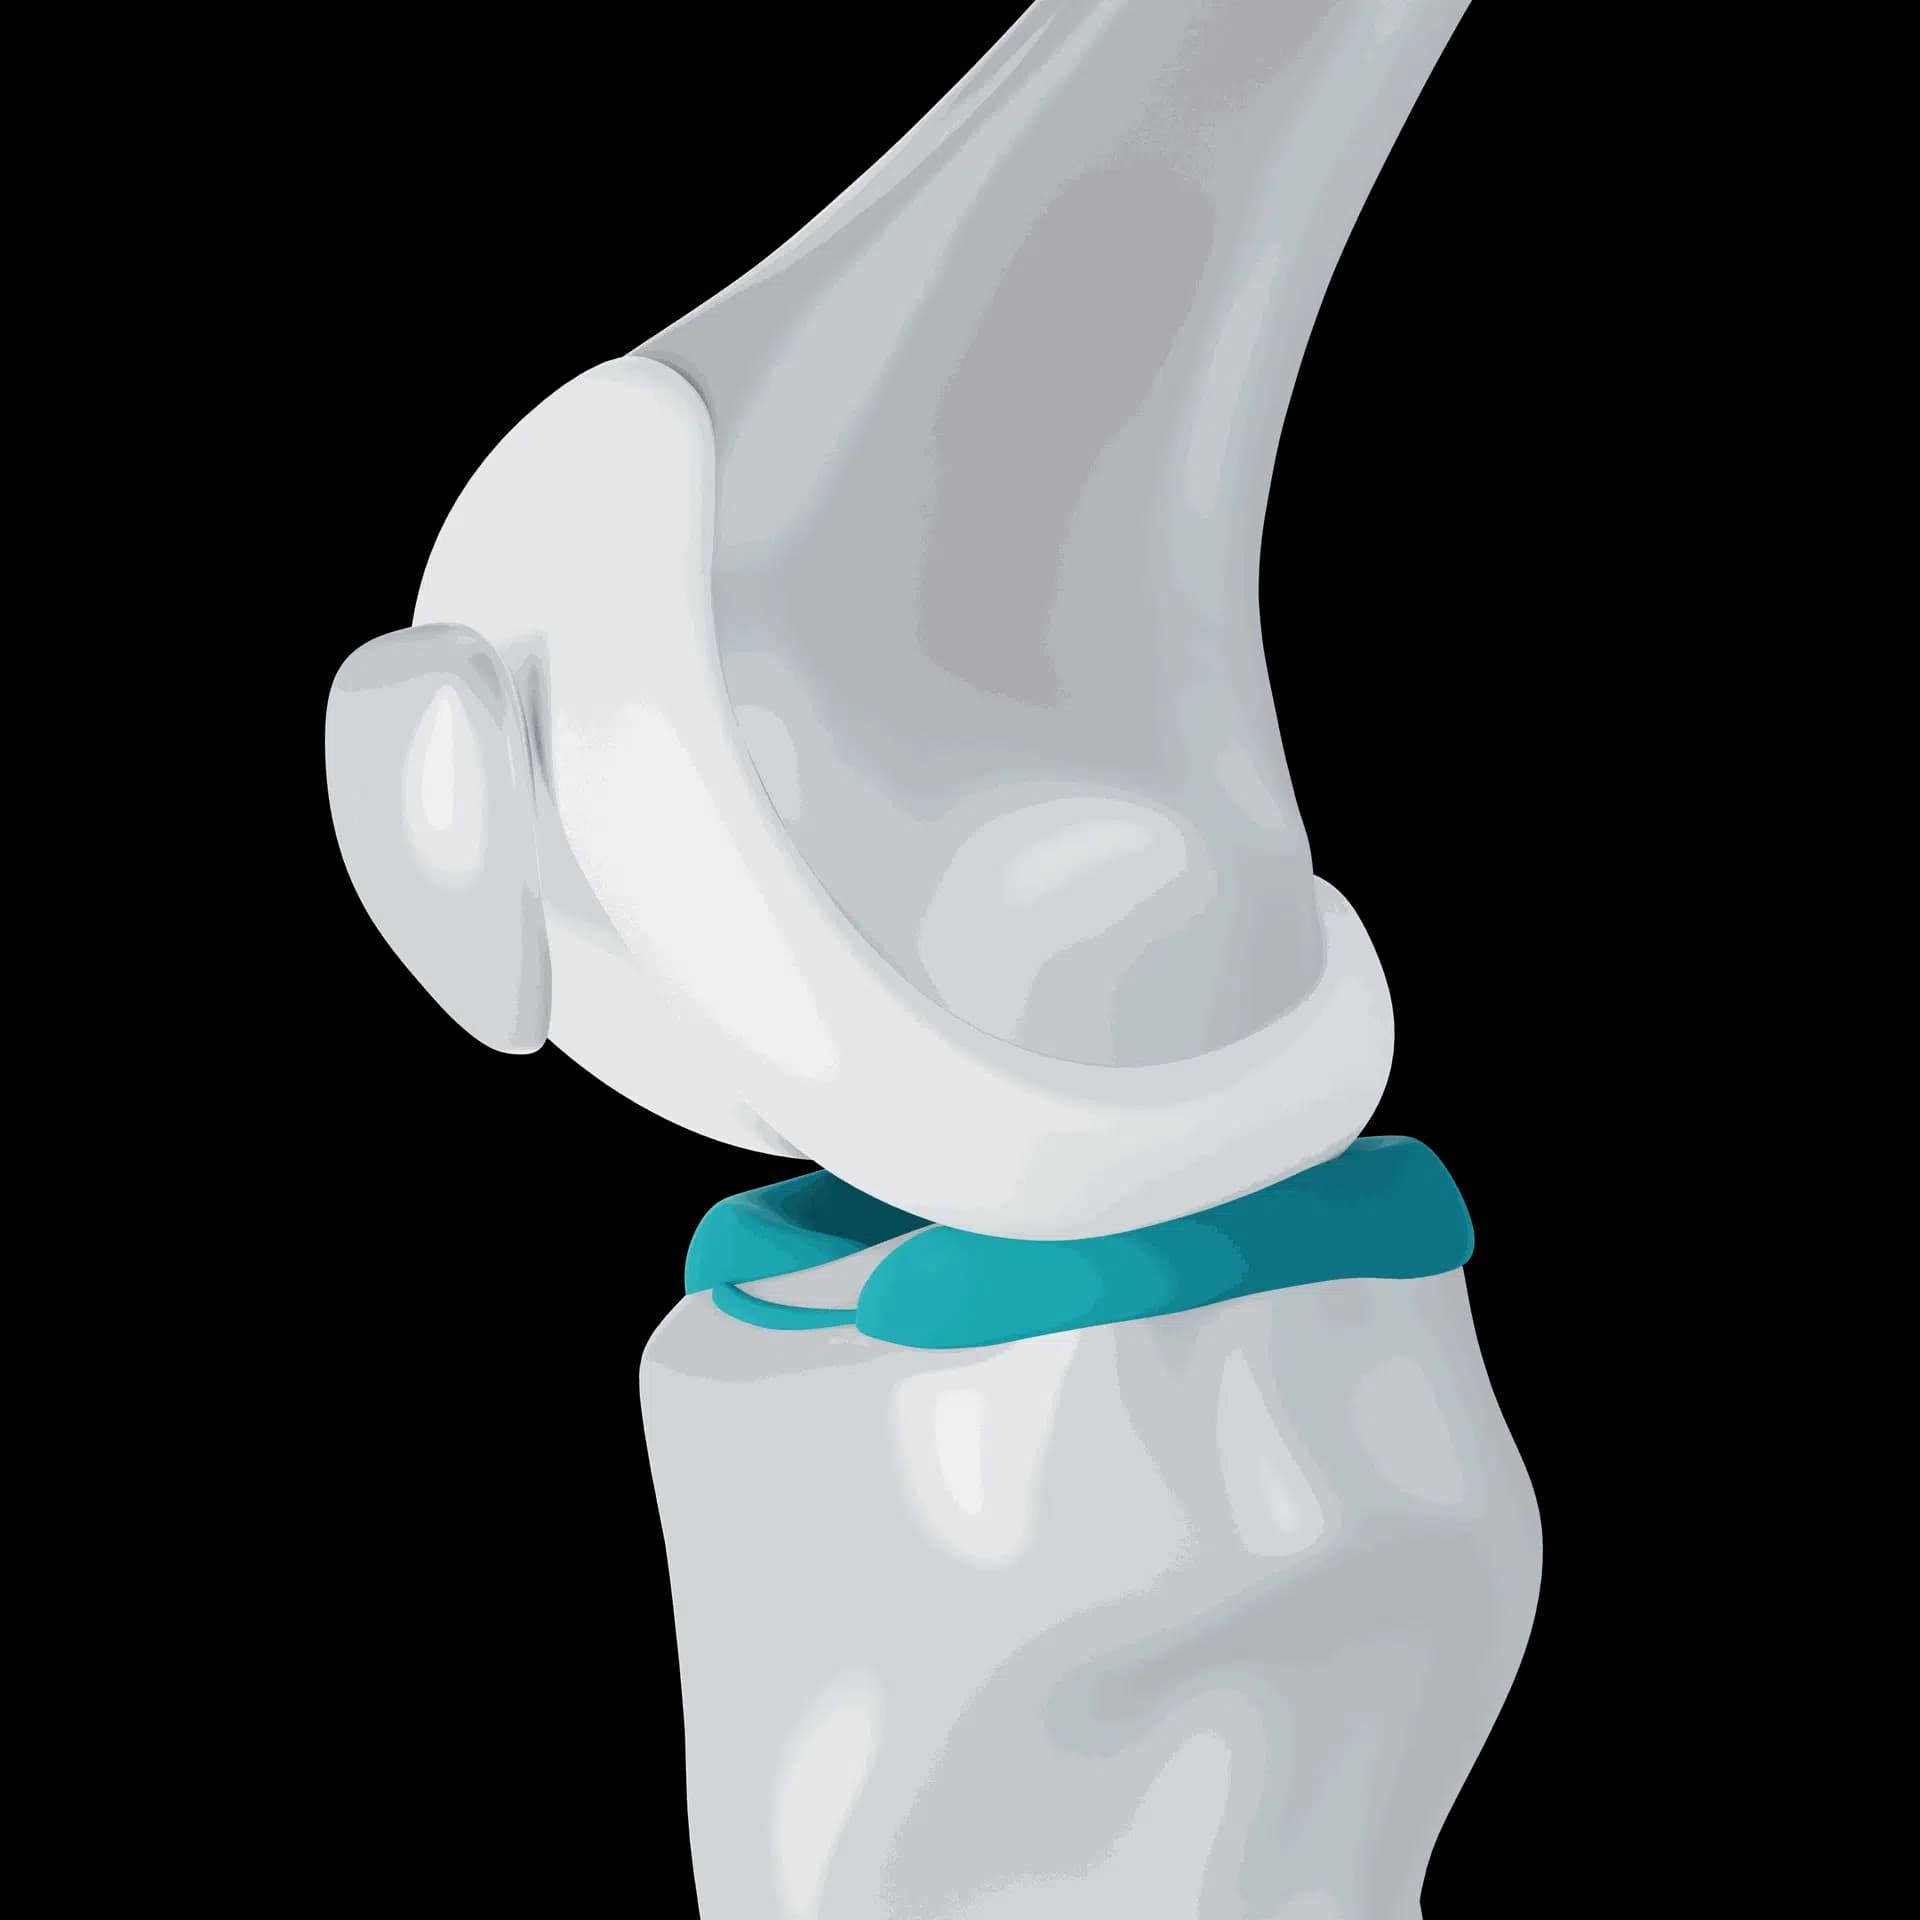
The tibial tubercle is the bony prominence at the top of the shin bone where the patellar tendon attaches. Its position controls the direction in which the quadriceps pulls the kneecap. If the tubercle sits too far to the outside, or the kneecap sits too high, the kneecap is pulled off course, which can lead to dislocations or uneven wear of the cartilage behind it.
In a tibial tubercle osteotomy (TTO), the surgeon cuts a carefully planned piece of bone carrying the tubercle, moves it a measured distance, and fixes it in the new position with screws. Depending on the problem, the tubercle may be moved inwards (medialisation), inwards and forwards (anteromedialisation, sometimes called a Fulkerson osteotomy), or downwards (distalisation) for a high-riding kneecap.
Who it may help
- Recurrent kneecap dislocation with an outward-placed tubercle, often measured as an increased TT-TG distance on scans
- A high-riding kneecap (patella alta) that does not engage the groove properly
- Pain from cartilage wear on the lower or outer part of the kneecap, in selected patients
- Failed previous kneecap stabilisation where alignment was not corrected
TTO is not a routine first operation for every unstable kneecap. Many patients are stabilised with MPFL reconstruction alone. It is also not suitable for children whose growth plates are still open, because the tubercle sits close to a growth area.
Assessment before surgery
Dr. Gelber examines how the kneecap moves, how loose the soft tissues are, the leg alignment and the rotation of the hips and shins. X-rays and an MRI, sometimes with a CT scan, measure the kneecap height, the shape of the groove, the tubercle position and the condition of the cartilage. These measurements guide whether the tubercle needs moving at all, in which direction and by how much, and whether other procedures should be combined.
The operation
The operation is performed under general or spinal anaesthesia, usually with an arthroscopy at the start to inspect the cartilage. Through an incision over the front of the upper shin, the tubercle is cut, repositioned and fixed with two or three screws. MPFL reconstruction or cartilage treatment are often performed at the same time. Most patients stay in hospital for one or two nights.
Recovery
- A hinged brace and crutches for around six weeks, with weight-bearing guided by the surgeon
- Early exercises to regain bending and keep the quadriceps working
- Bone healing usually takes around six to eight weeks, confirmed on X-ray
- Desk work after roughly two to six weeks, depending on comfort and travel
- Driving once you can control the leg safely and are off crutches
- Running and sport usually after several months, often around four to six months for many patients, guided by strength and control
The screws may cause tenderness when kneeling and are sometimes removed later. Physiotherapy is central to the result.
Risks
Risks include delayed or non-healing of the bone cut, fracture of the shin bone if it is loaded too early, irritation from the screws, stiffness, infection, blood clots, numbness around the scar and, rarely, nerve or vessel injury. Following the weight-bearing instructions carefully reduces the risk of fracture. Smoking slows bone healing and should be stopped well before surgery.
Kneecap realignment at Aman Hospital in Doha
If your kneecap keeps slipping out, or you have persistent kneecap pain with known alignment problems, Dr. Gelber can assess whether TTO is needed or whether a simpler operation or rehabilitation is enough. Bring any previous scans and operation notes. Surgery can be planned around exams, sports seasons, Ramadan and the summer months in Qatar.
Frequently asked questions
Do I need a TTO or just an MPFL reconstruction?
It depends on your measurements. If the main problem is a torn or loose MPFL and alignment is acceptable, MPFL reconstruction alone is often enough. TTO is added when the tubercle position or kneecap height is clearly abnormal, or when kneecap cartilage needs unloading.
Will I be able to kneel and pray normally afterwards?
Kneeling directly on the front of the knee can stay uncomfortable for months, partly because of the screws. Many patients find sujood manageable once the bone has healed, and praying on a chair is a practical option during recovery.
Will the screws need to be removed?
Not always. They are removed only if they cause tenderness or irritation, usually after the bone has fully healed, often a year or more later.
Can I fly home after a TTO?
Long flights soon after leg surgery increase the risk of blood clots. Discuss your travel dates with the team, who will advise on timing, movement during the flight and whether clot prevention is needed.
Glossary
Patients also ask
- When can I kneel, sit on the floor and pray normally after a tibial tubercle osteotomy?
- My screws hurt when I kneel after a tibial tubercle osteotomy. Should they come out?
- What are the risks of a tibial tubercle osteotomy?
- What is recovery like after a tibial tubercle osteotomy, week by week?
- What is a tibial tubercle osteotomy?
- My surgeon says I need my shinbone cut to fix my kneecap. Why?
Related