Procedures
ACL Repair: Ligament-Preserving Surgery for Selected Tears
Quick answer
ACL repair reattaches your own torn ligament to the bone instead of replacing it with a graft. It suits only a minority of tears, mainly fresh tears close to the thigh bone with good-quality tissue, and its long-term results are still being studied, explains Dr. Pablo Gelber, knee surgeon at Aman Hospital in Doha.
What is ACL repair?
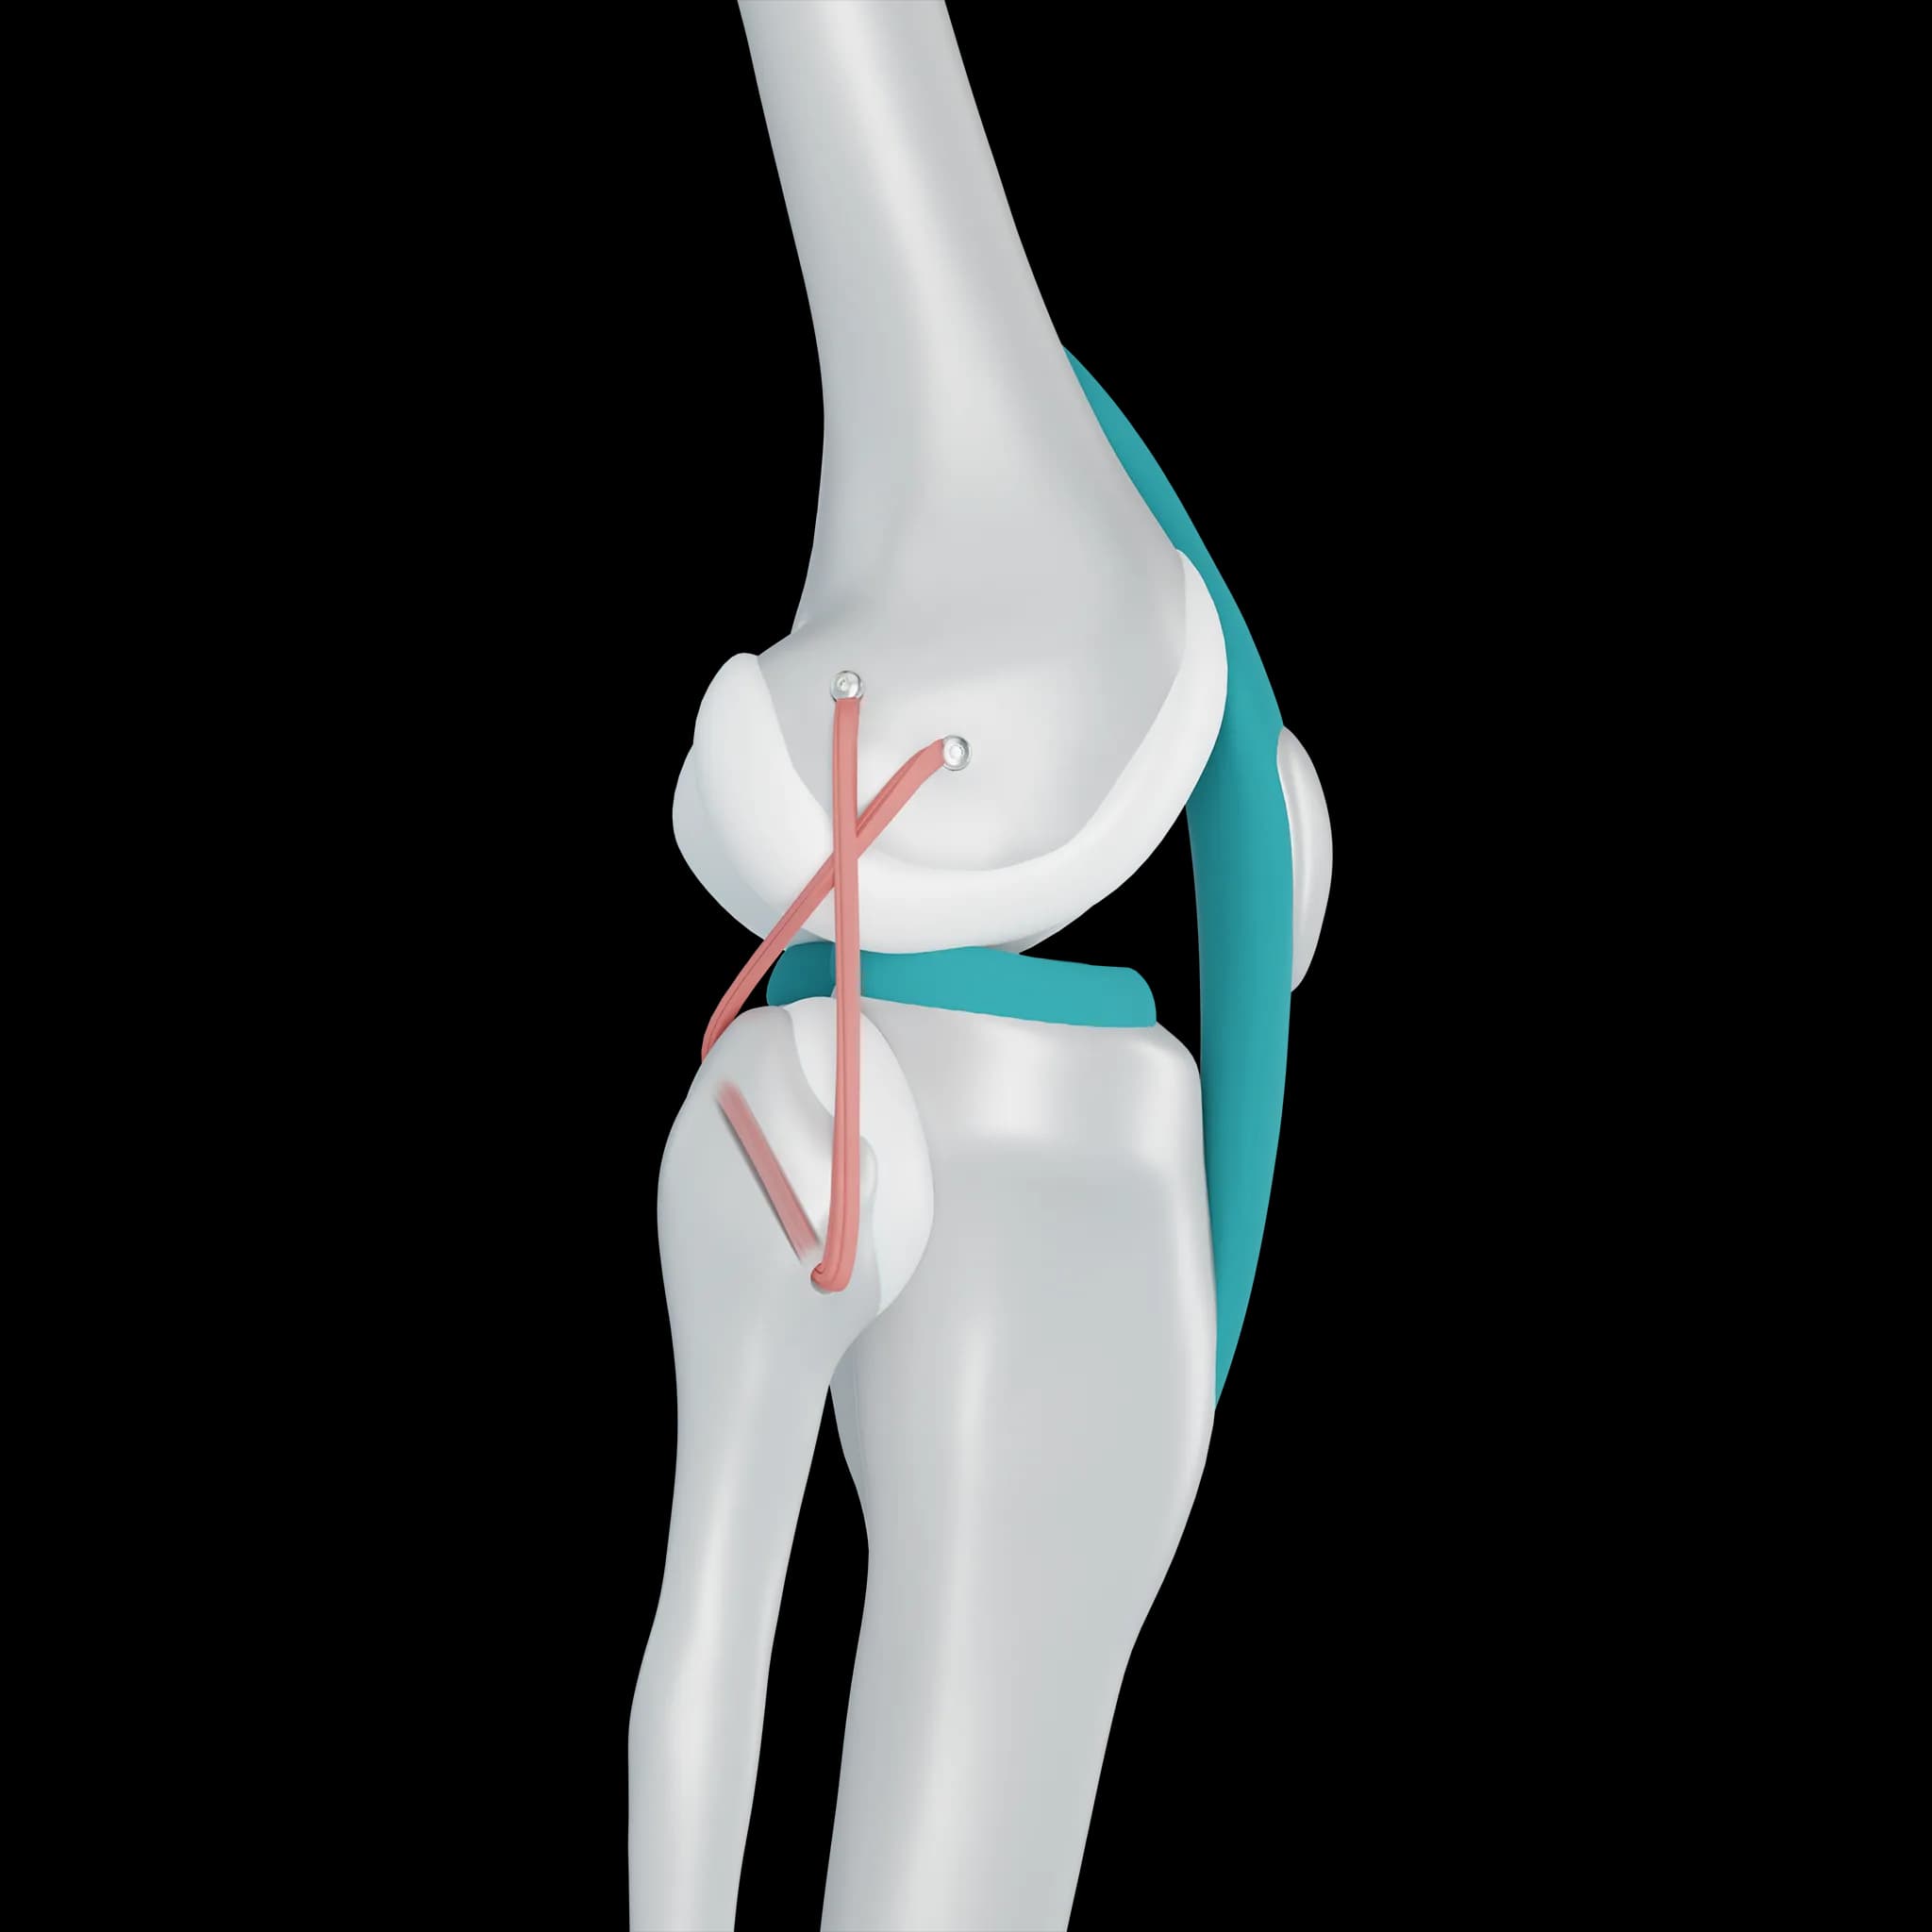
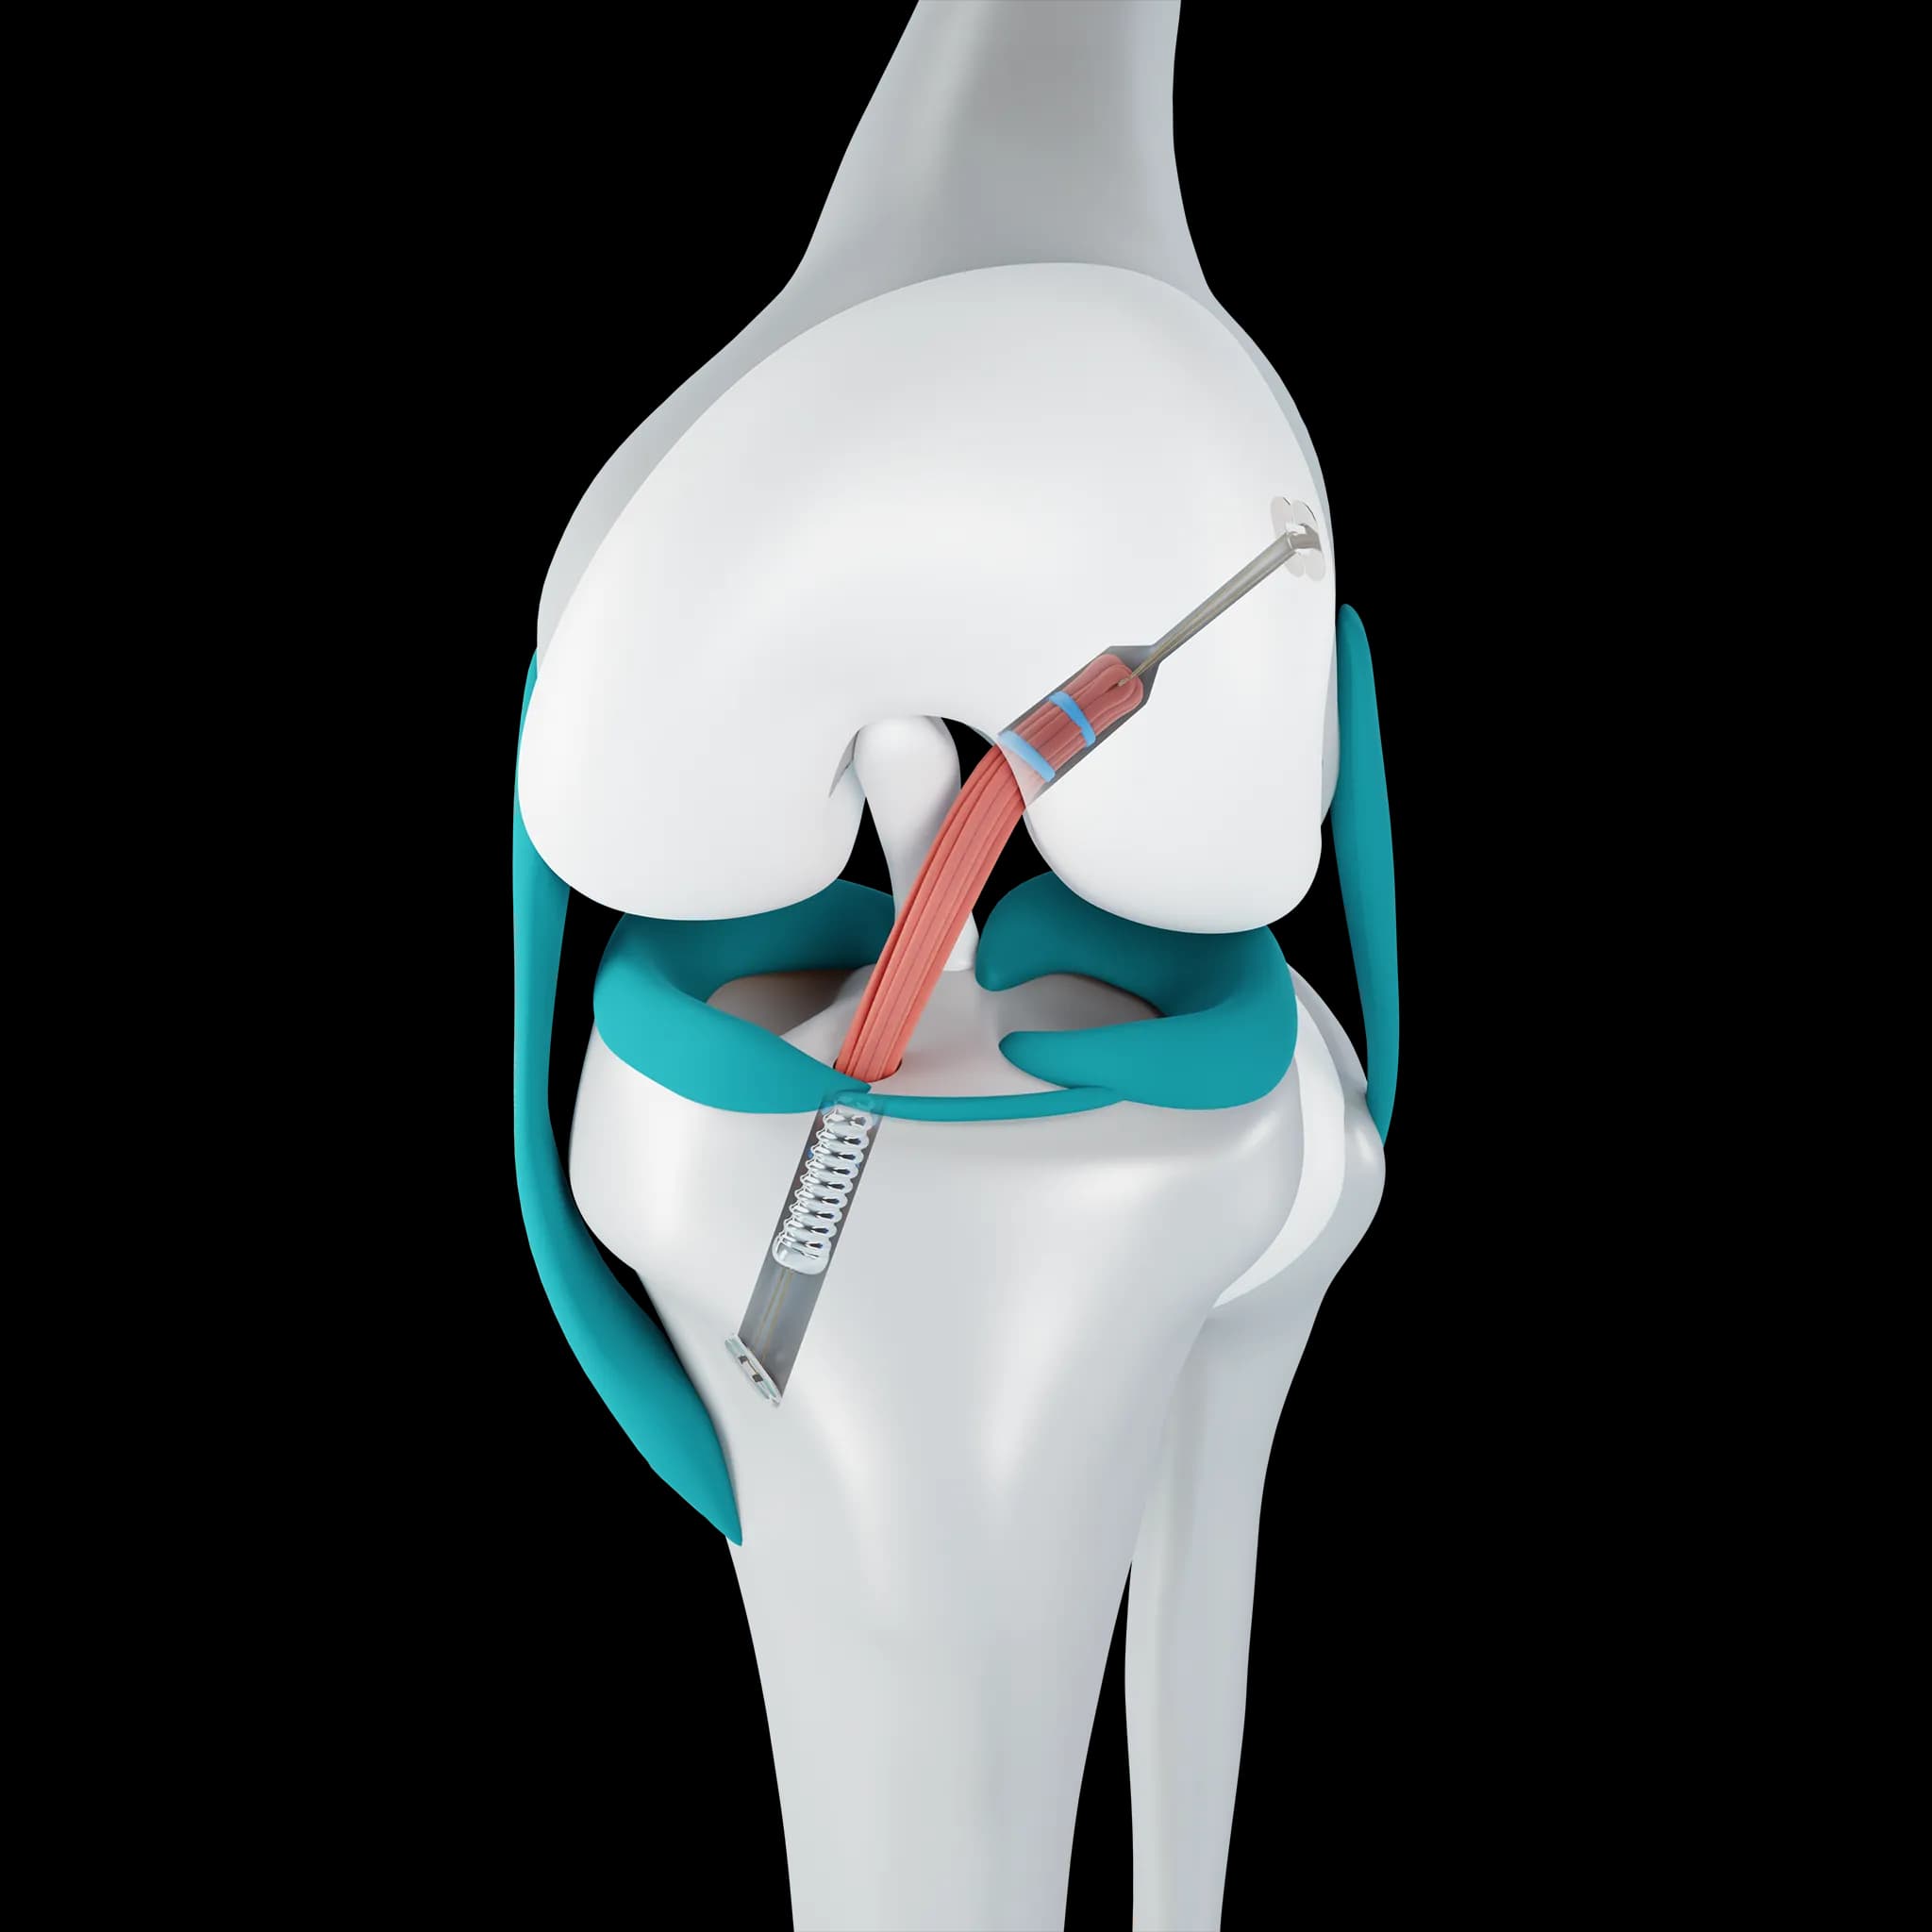
In standard ACL reconstruction, the torn ligament is removed and replaced with a tendon graft. ACL repair takes a different approach: the surgeon stitches the patient's own ligament and fixes it back to its attachment on the thigh bone, usually with a small anchor. The repair is often protected with a strong synthetic tape running alongside it while the ligament heals.
Attempts to repair the ACL were abandoned decades ago because results were poor. Interest has returned because MRI, arthroscopy and fixation devices have improved, and because surgeons now select patients much more carefully, focusing on tears that have a better chance of healing.
Who may be suitable
- A tear at or very near the ligament's upper attachment on the thigh bone, rather than in the middle of the ligament
- Good-quality ligament tissue that is long enough to reach the bone
- Surgery within the first few weeks after injury, before the ligament stump shrinks or scars
- A knee without major associated ligament injury or poor alignment
Only a minority of ACL tears meet these criteria. Most tears are in the middle of the ligament or have frayed tissue, and these are treated with reconstruction or a structured physiotherapy programme. MRI gives a strong indication, but the final decision is often made during arthroscopy, when the surgeon sees and tests the tissue directly. For this reason, patients consent to reconstruction as a backup if the ligament proves unsuitable.
Possible advantages
Because no graft is harvested, there is no pain or weakness at a donor site, such as the hamstrings or the patellar tendon. The operation is usually shorter and less invasive, and some patients regain movement and strength faster in the early weeks. Keeping the native ligament may preserve its nerve fibres, which play a role in knee position sense, although the clinical importance of this is still debated. If the repair fails, a standard reconstruction is usually still possible, as only small bone tunnels or anchors have been used.
What the evidence shows, honestly
Evidence on modern ACL repair is evolving. Studies in carefully selected patients report encouraging short- and mid-term results, but many are small, and long-term data are limited. Several studies have found higher re-tear or revision rates after repair than after reconstruction, particularly in young patients returning to pivoting sports such as football and basketball.
For this reason, repair is not presented as a replacement for reconstruction. It is an option for a specific tear pattern, to be discussed openly with a surgeon who performs both operations and can explain the trade-offs for your age, sport and goals.
Recovery
- Walking with crutches from the first day, often with a brace for the early weeks
- Early focus on swelling control, full straightening and quadriceps activation
- Strength and balance work progressing over the first three months
- Running usually reintroduced around three to four months, once strength and control allow
- Return to pivoting sport based on strength and functional testing, not the calendar
Even if early recovery feels quicker, the healing ligament needs time. Most surgeons follow return-to-sport criteria similar to those after reconstruction, and patients in Qatar can plan rehabilitation around the summer heat by training indoors.
Risks
Risks include re-tear or persisting looseness, stiffness, infection, blood clots and the need for further surgery. These are discussed in detail before consent, along with the possibility of converting to reconstruction during the operation.
Discussing ACL repair in Doha
Timing matters, so if you have just injured your knee and are interested in a ligament-preserving option, arrange an early assessment and MRI. At Aman Hospital, Dr. Gelber reviews the tear pattern, tissue quality and your goals, and explains whether repair, reconstruction or non-surgical treatment suits your knee.
Frequently asked questions
Is ACL repair better than reconstruction?
Not in general. Repair suits a specific type of fresh tear near the thigh bone and avoids taking a graft, but reconstruction has longer and more established results, especially for young athletes in pivoting sports. The right choice depends on the tear and your goals.
My ACL tear is several months old. Can it still be repaired?
Usually not. Over time the ligament stump tends to shrink and scar, which makes repair unreliable. Older tears are generally treated with reconstruction or rehabilitation, depending on symptoms.
Will my MRI show whether I can have a repair?
MRI shows where the tear is and gives a good indication, but tissue quality is confirmed during arthroscopy. That is why the surgical plan includes reconstruction as a backup.
Do children have ACL repair?
Ligament-preserving techniques are sometimes considered in children and teenagers with suitable tears and open growth plates, but this is a specialised decision made case by case after careful assessment.
Glossary
Patients also ask
- How long is recovery after ACL repair, and is it faster than reconstruction?
- Does ACL repair fail more often than reconstruction?
- My MRI says my ACL tore off the bone. Can it be repaired?
- My teenager tore their ACL. Is repair an option instead of reconstruction?
- What is ACL repair, and how is it different from ACL reconstruction?
- Why does ACL repair have to be done soon after the injury?
Related