Conditions
Knee Dislocation and Multi-Ligament Injury in Doha
Quick answer
A knee dislocation happens when the thigh and shin bones are forced apart, tearing two or more major ligaments and sometimes injuring the artery or nerve behind the knee. It is an emergency first, then a reconstruction problem. Dr. Pablo Gelber at Aman Hospital in Doha plans multi-ligament surgery and rehabilitation once the limb is safe.
What is a knee dislocation?
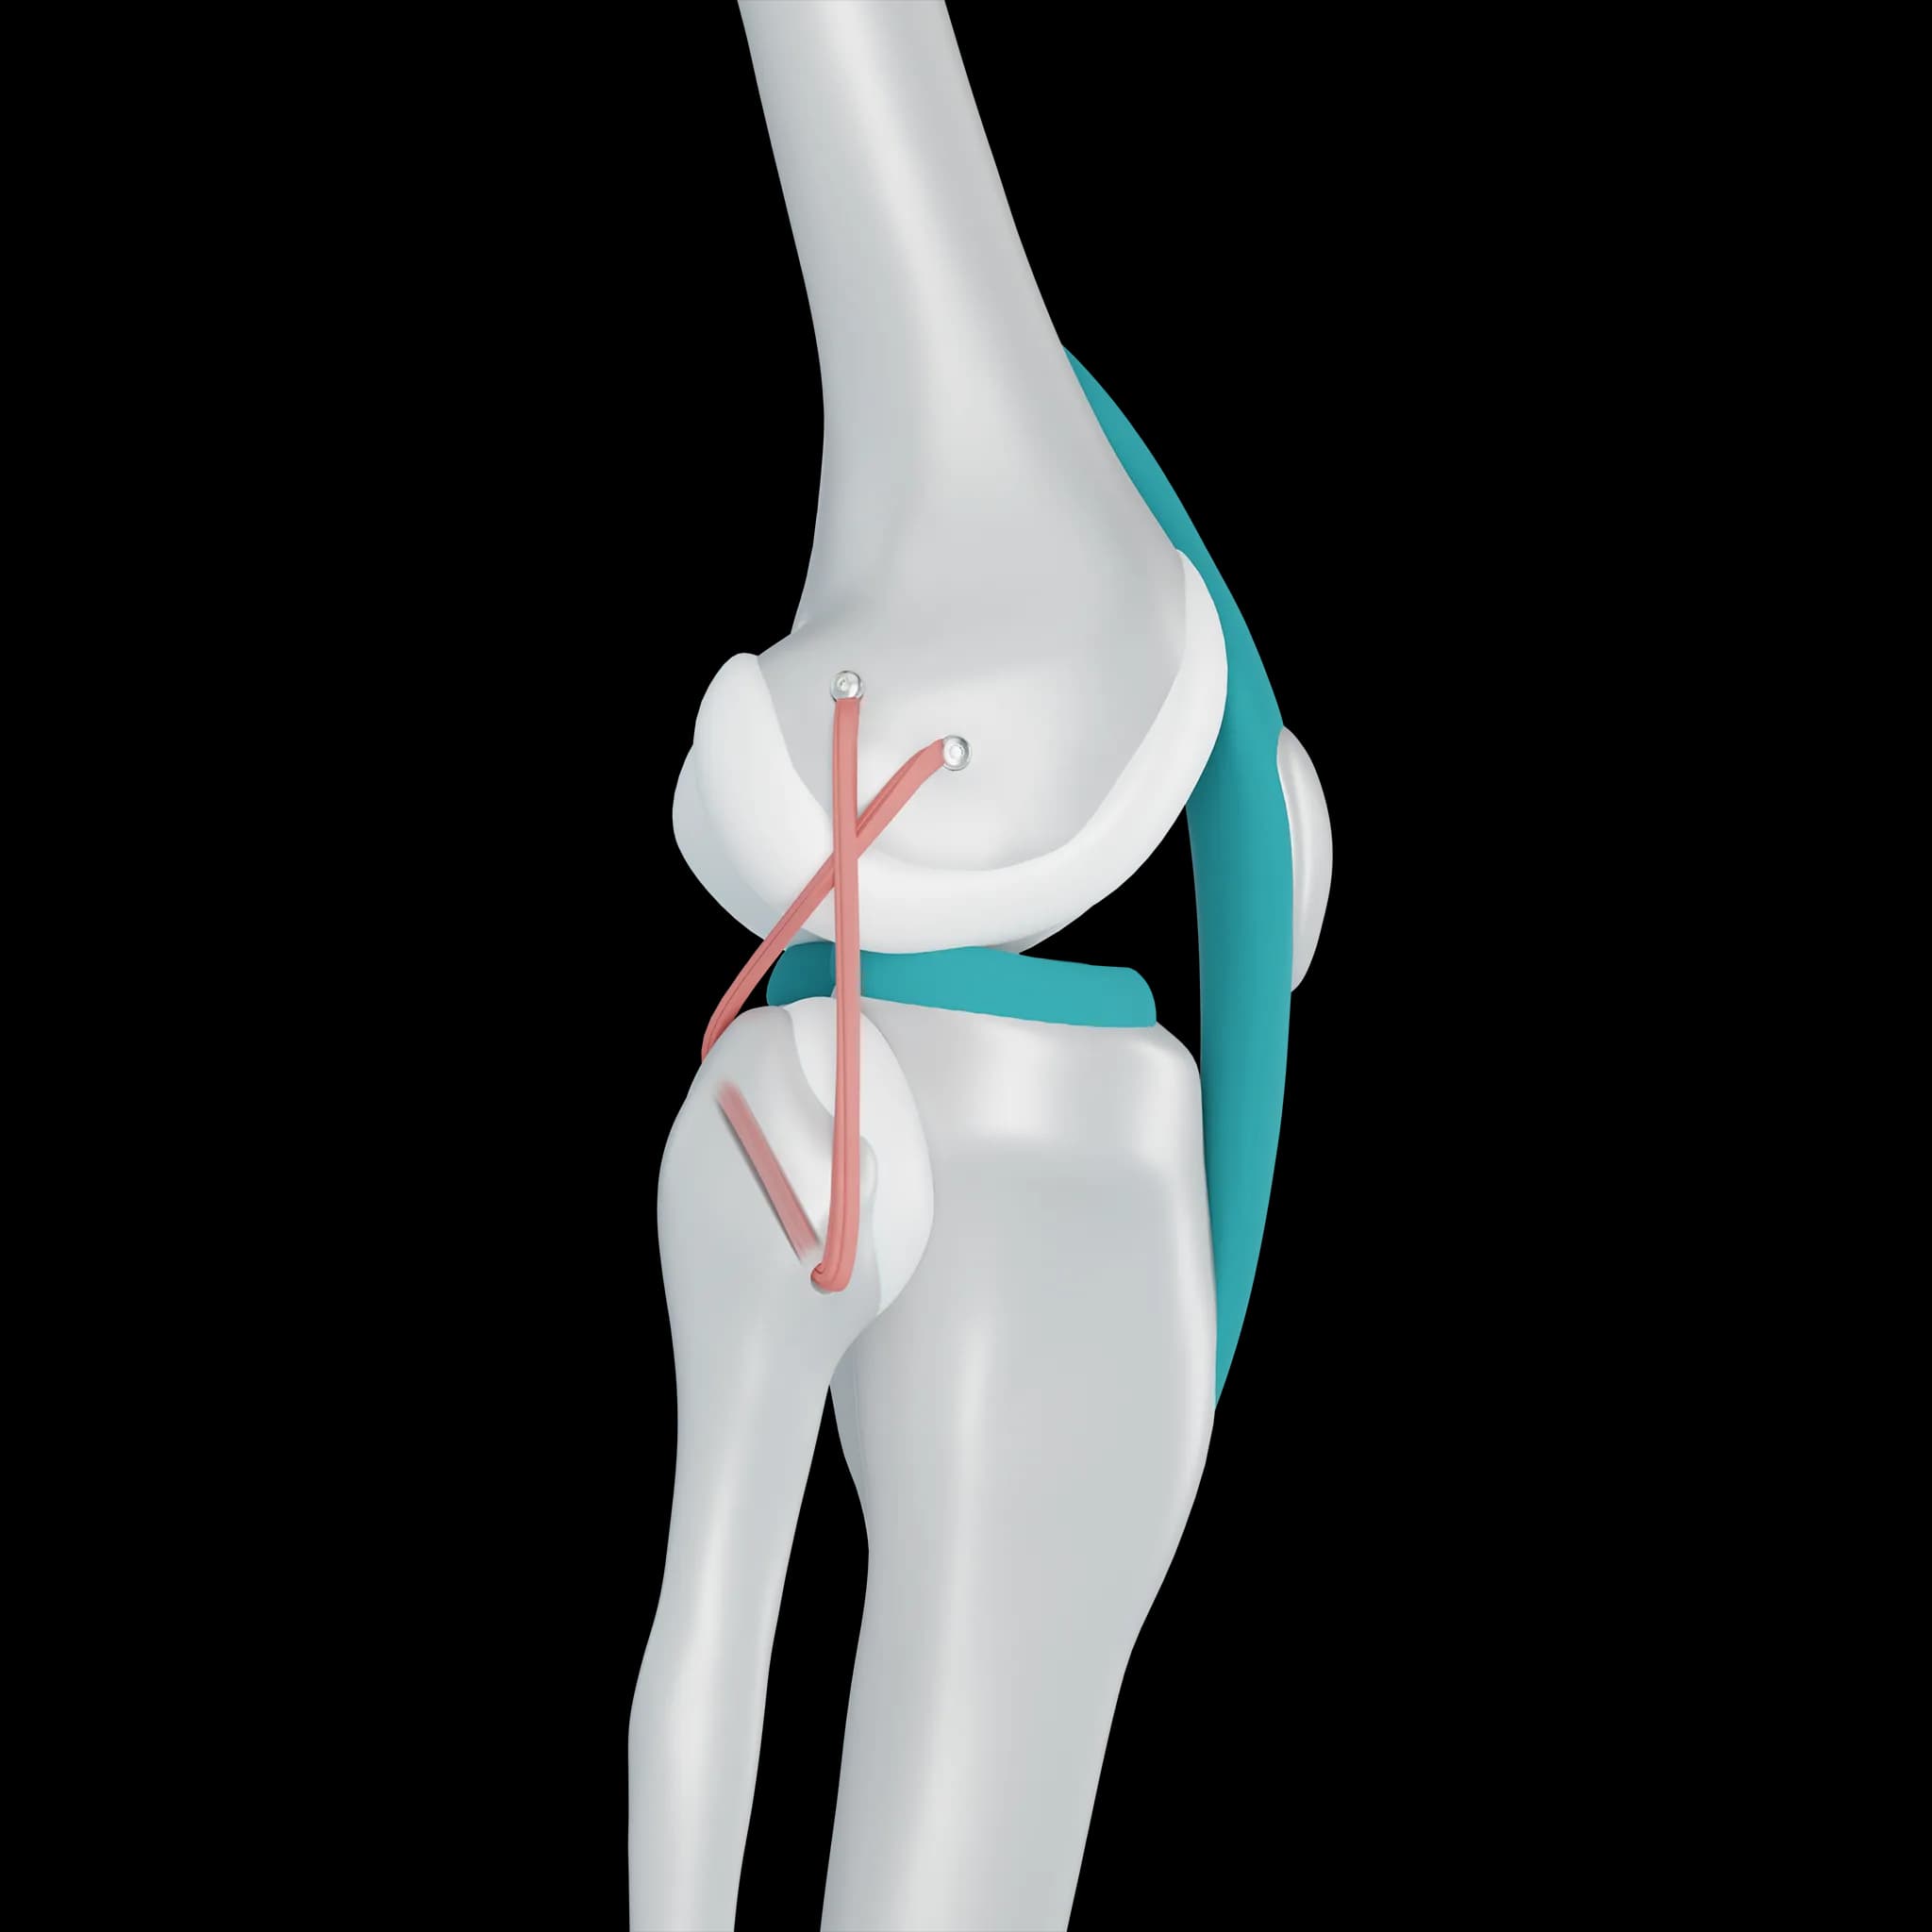
In a knee dislocation, the tibia (shin bone) moves completely out of contact with the femur (thigh bone). This is different from a kneecap dislocation, which is far more common and less serious. To dislocate the knee joint itself, at least two of the four main ligaments must tear: the ACL, PCL, MCL and the lateral collateral ligament with the posterolateral corner.
Many knees put themselves back in place before the patient reaches hospital, so a knee that looks normal on arrival can still have had a dislocation. Any knee with two or more torn ligaments is treated as a possible dislocation until proven otherwise.
Why it is an emergency
The popliteal artery and the peroneal nerve run close behind and beside the knee. In a dislocation they can be stretched or torn. An artery injury can threaten the leg if it is not recognised quickly, even when the foot initially looks normal.
Go straight to an emergency department, or call 999 in Qatar, if after a knee injury:
- The knee looks deformed or out of place
- The foot is cold, pale or blue, or the pulse in the foot is weak
- There is numbness, or you cannot lift the foot or toes
- Pain in the calf is severe and getting worse, or the leg is very tight and swollen
In the emergency department, the knee is put back in place if needed, pulses are checked and the ankle-brachial index or a CT angiogram is used to assess the artery.
Causes and who gets it
High-energy knee dislocations follow road traffic collisions, motorbike accidents and falls from height. In Qatar these include highway collisions, quad bike and dune bashing accidents in the desert, and falls on construction and industrial sites.
Lower-energy dislocations happen in sport, such as football, judo, wrestling and rugby, and occasionally from a simple fall in people with a high body weight. Lower-energy injuries can still damage the artery and nerve.
How the injury is mapped
Once the limb is safe, Dr. Gelber builds a full picture of the injury before planning surgery:
- Careful examination of each ligament, often repeated once the pain and swelling settle
- An MRI scan to show every torn ligament, the menisci, cartilage and tendons
- X-rays and sometimes CT to detect fractures, including avulsion fragments
- Nerve assessment, and nerve studies later if there is foot weakness
- Review of the vascular findings from the emergency team
The pattern of injury, for example ACL plus PCL, or PCL plus posterolateral corner, guides which structures need repair or reconstruction and in what order.
Treatment
Almost all true knee dislocations need surgery to restore a stable, functional knee. Treatment is individual, but usually follows these principles:
- Emergency care first: reduction, artery repair if needed, and sometimes a temporary external frame to hold the knee
- Early repair or reconstruction of the outer and inner corners, often within the first few weeks, because these structures heal poorly when left
- Reconstruction of the cruciate ligaments, either at the same operation or in a second stage
- Protecting the meniscus and cartilage, which carry the knee for the rest of life
Some patients with lower-demand lifestyles or other health problems may be treated with a brace and rehabilitation, accepting some looseness.
Recovery and long-term outlook
Recovery from a multi-ligament injury is long. Patients typically use crutches and a brace for six to twelve weeks, work hard on regaining full straightening and bending, and rebuild strength over many months. Return to desk work may be possible within a few months; heavy manual work and sport often take nine to twelve months or more.
Stiffness is a common challenge, so early, guided physiotherapy matters. Many patients regain a stable knee for daily life and work, and some return to sport. Over the long term there is a higher risk of arthritis, which is why follow-up continues after rehabilitation.
When to see a knee specialist in Doha
After emergency care, ask for a specialist review if you have been told several ligaments are torn, if your knee was described as dislocated, or if your knee still feels loose in several directions months after an accident. Dr. Gelber manages complex ligament injuries at Aman Hospital in Doha and works with physiotherapists on a staged recovery plan.
Frequently asked questions
Is a dislocated knee the same as a dislocated kneecap?
No. A kneecap dislocation means the patella slips out of its groove and is much more common. A knee dislocation means the main joint between the thigh and shin has come apart, tearing several ligaments, and is a far more serious injury.
Will I need more than one operation?
Sometimes. Some multi-ligament injuries are reconstructed in one operation, while others are staged, for example fixing the corners first and the cruciate ligaments later. The plan depends on the injury pattern, skin, swelling and other injuries.
Will I be able to kneel for prayer again?
Many patients regain enough bending to pray, though deep kneeling and sujood may take many months to return, and some use a chair long term. Regaining knee bend is a key goal of rehabilitation.
Can I fly home after a knee dislocation?
Long flights after major knee injury or surgery raise the risk of blood clots. Timing, clot prevention and seating should be discussed with your surgeon before booking travel.
Glossary
Patients also ask
- How do knee dislocations and multi-ligament injuries happen?
- Is a dislocated knee the same as a dislocated kneecap?
- My knee bent backwards and now it feels completely unstable. Have I torn more than one ligament?
- What should I do if I think my knee has dislocated?
- Why do doctors check the artery and nerves after a knee dislocation?
Related