Procedures
Multi-Ligament Knee Reconstruction in Doha
Quick answer
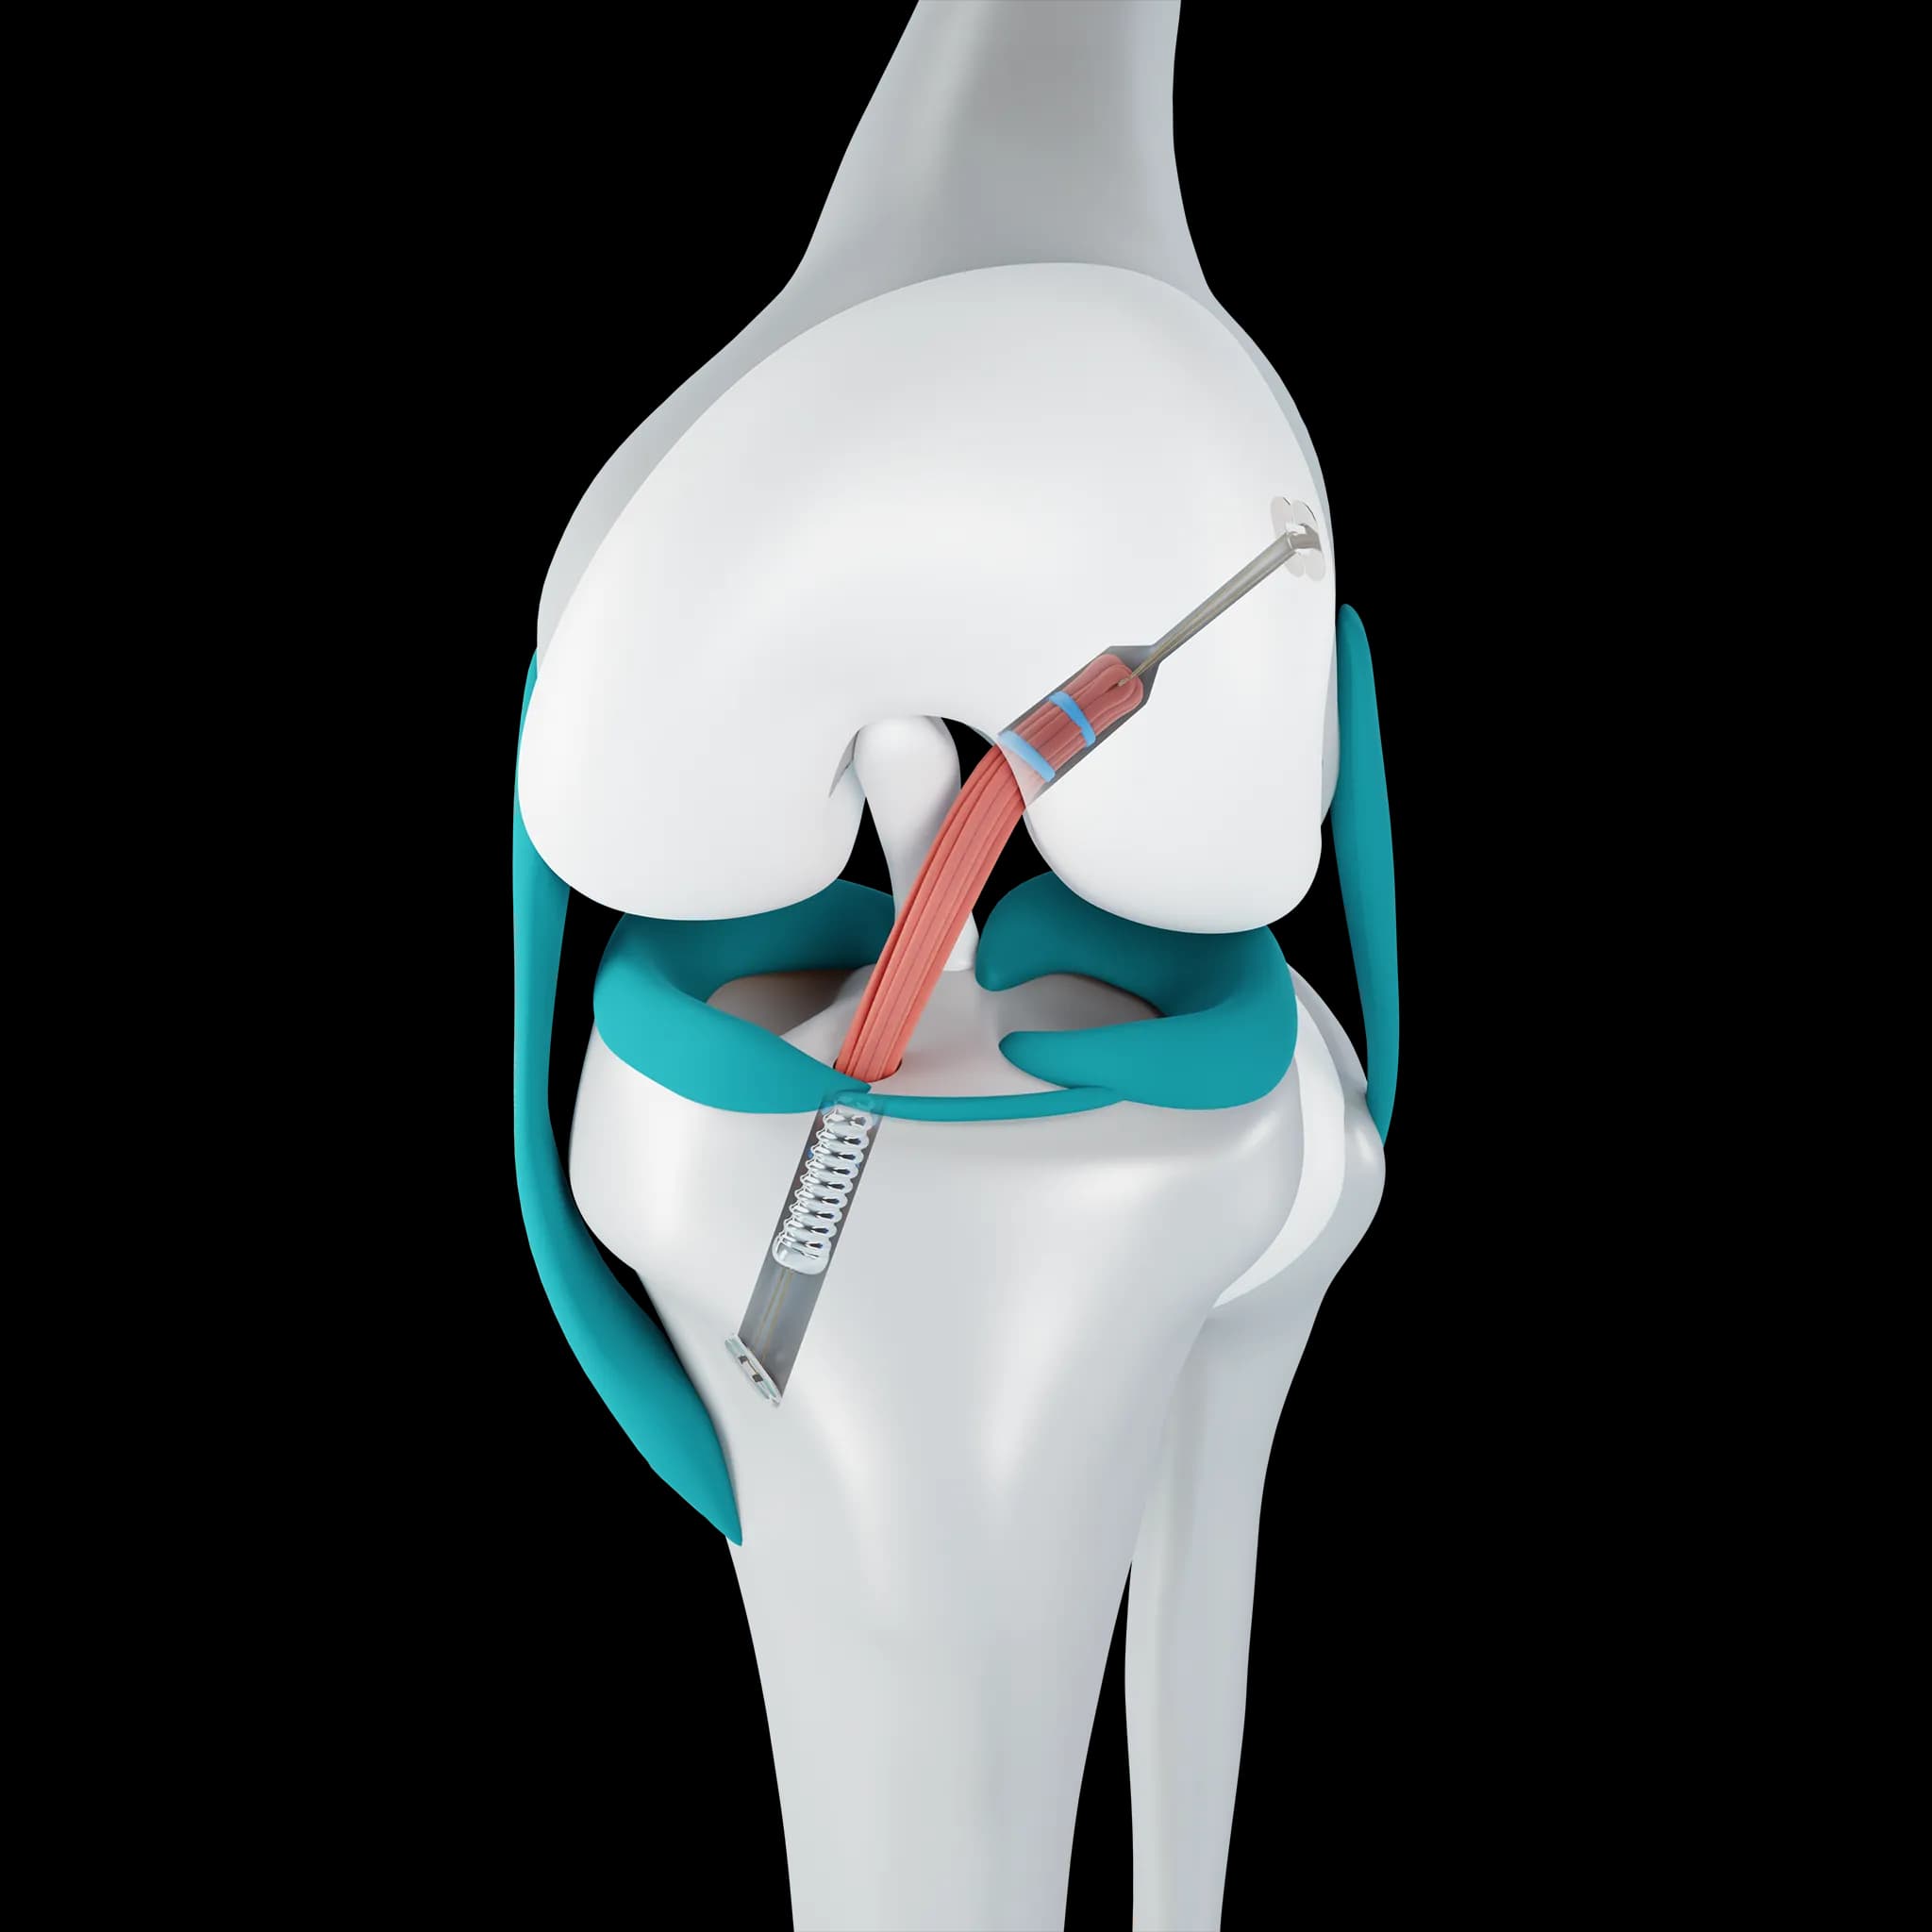
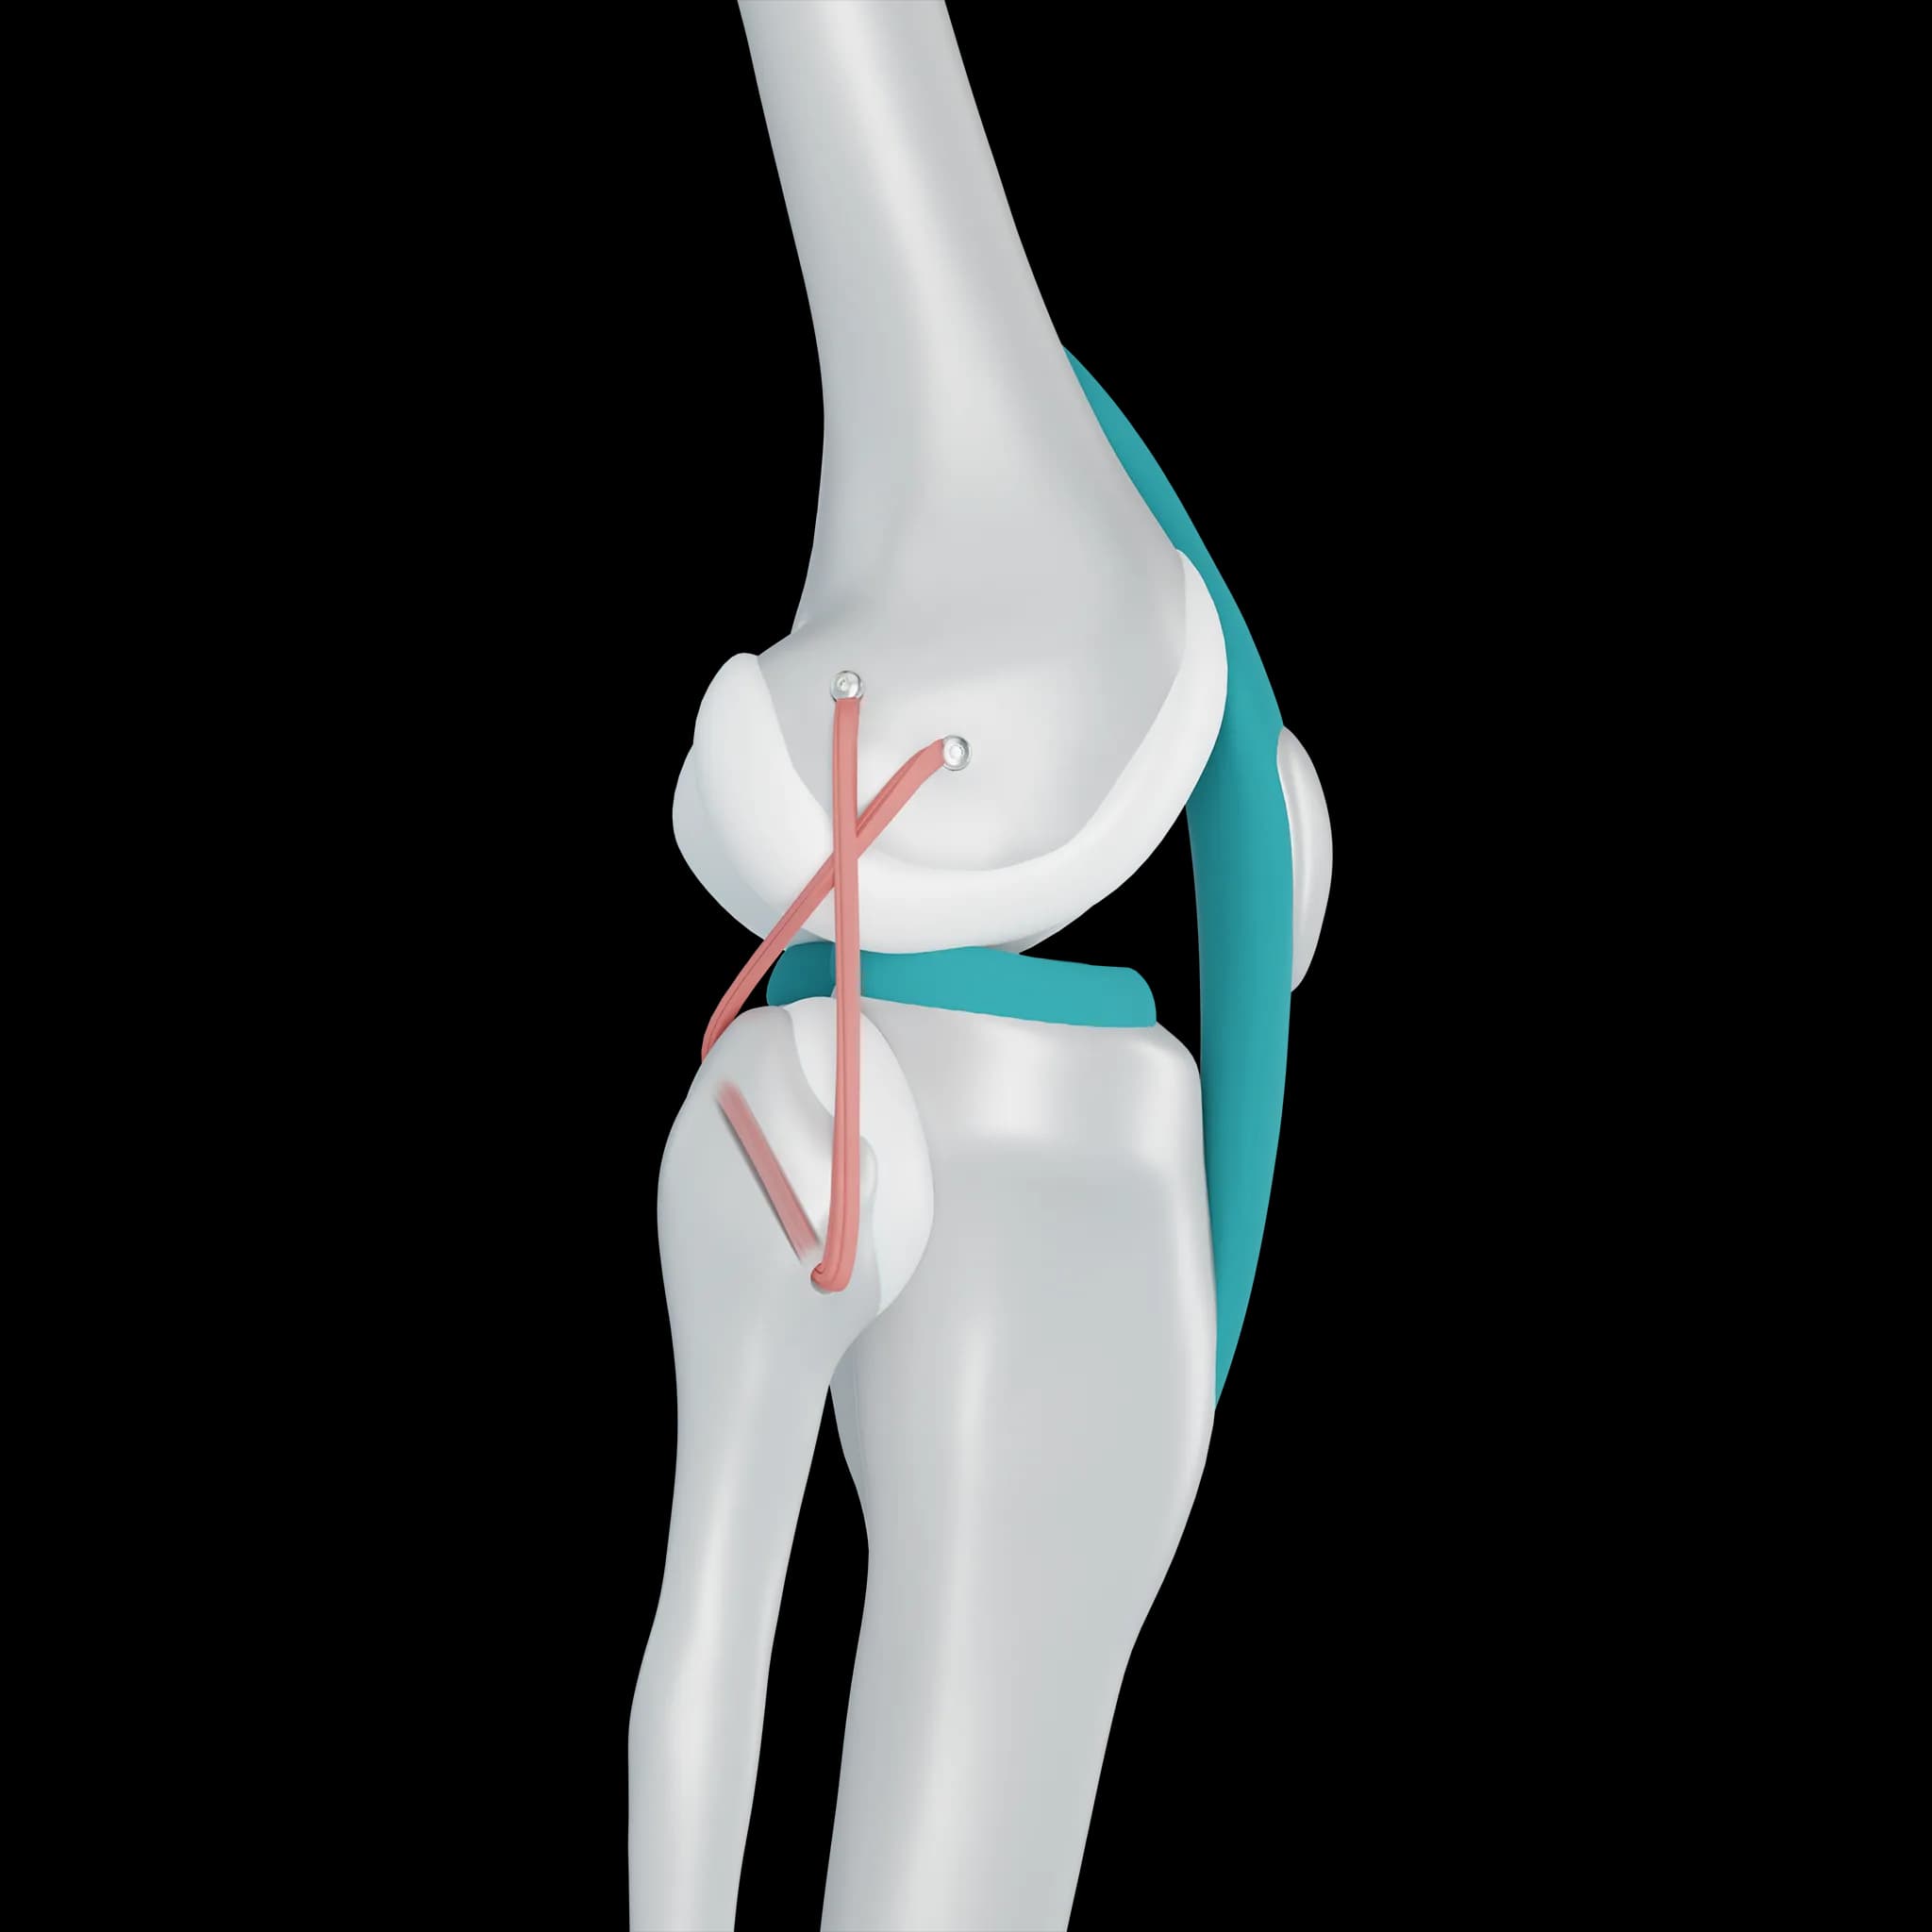
Multi-ligament reconstruction rebuilds two or more torn knee ligaments, such as the ACL, PCL and the inner or outer corners, so the knee is stable in every direction. It is planned after the limb is safe and is followed by months of structured rehabilitation, explains knee surgeon Dr. Pablo Gelber at Aman Hospital, Doha.
When is it needed?
Multi-ligament reconstruction is used when two or more of the knee's main stabilisers are torn. This most often follows a knee dislocation from a road traffic collision, a fall from height, a motorbike or quad bike accident, or a high-energy sports injury.
Common patterns include the ACL with the PCL, the ACL with the posterolateral corner, the PCL with the posterolateral corner, and injuries to three or four ligaments. Without surgery, most of these knees remain loose and give way, which damages the meniscus and cartilage over time.
Planning the operation
Every multi-ligament knee is different, so planning is detailed. It usually includes:
- Confirming that the artery and nerves have been assessed and are safe
- Repeated examination of each ligament, ideally once pain allows
- An MRI scan to map torn ligaments, the meniscus, cartilage and tendons
- X-rays or CT to detect fractures and to check leg alignment and tibial slope
- A plan for which graft to use for each ligament, from the patient's own tendons or donor tissue
- Agreement on timing: one operation, or a staged approach
The skin and soft tissues must be in good condition before major reconstruction. Swelling, blisters or wounds may delay surgery.
Single-stage or staged surgery
Many surgeons repair or reconstruct the inner or outer corners early, often within the first two to three weeks, because these structures heal poorly when left and are easier to repair while fresh. The cruciate ligaments can be reconstructed at the same time, or in a second operation once the knee has regained movement.
Single-stage surgery means one anaesthetic and one recovery. Staged surgery may lower the risk of stiffness and allows the knee to settle between steps. The choice depends on the injury pattern, the state of the skin, associated fractures, the patient's other injuries and surgeon judgement. Dr. Gelber explains the reasoning for each patient.
What the surgery involves
The operation combines arthroscopic and open techniques. Cruciate ligaments are usually reconstructed through small incisions with tendon grafts passed through bone tunnels. Corner injuries usually need an open incision on the inner or outer side of the knee to repair or reconstruct the collateral ligaments and supporting structures, and to protect the peroneal nerve on the outer side.
Tunnels are positioned so that they do not collide, and grafts are tensioned in a specific order to restore the knee's normal resting position. Torn menisci are repaired where possible. The operation can take several hours, and a short hospital stay is usual.
Rehabilitation and recovery
Recovery is long and follows clear phases, adjusted for which ligaments were reconstructed:
- Weeks 0 to 6: a brace locked or limited in range, crutches with protected weight bearing, and early work on full straightening
- Weeks 6 to 12: gradual weight bearing, increasing bend, quadriceps strengthening and cycling
- Months 3 to 6: strength, balance and walking without a limp
- Months 6 to 9: running and agility, if strength allows
- Around 9 to 12 months or longer: return to heavy manual work or sport, guided by testing
Stiffness is the most common problem after multi-ligament surgery, so attendance at physiotherapy is essential. Some patients need a further minor procedure to improve movement.
Risks and outcomes
Risks include stiffness, residual looseness, infection, wound problems, blood clots, nerve irritation and, rarely, injury to blood vessels. Patients with a nerve injury from the original trauma may have lasting foot weakness, which is managed separately.
Many patients regain a stable knee for walking, stairs, work and daily life. Return to high-level pivoting sport is possible for some, but less predictable than after a single ligament reconstruction. The risk of arthritis later in life is higher than in an uninjured knee, so long-term follow-up is advised.
Practical points for patients in Qatar
Patients often need help at home for the first weeks, a ground-floor or lift-access setup, and time off manual work. Praying on a chair is usual during recovery. Long-haul flights should be discussed early because of clot risk, and rehabilitation in summer is usually scheduled indoors.
Dr. Gelber performs multi-ligament reconstruction at Aman Hospital in Doha. Costs vary with the number of ligaments, grafts, implants and length of stay, so check coverage with Aman Hospital and your insurer.
Frequently asked questions
How soon after a knee dislocation is reconstruction done?
Emergency treatment comes first. Repair of the inner or outer corners is often done within the first few weeks, and cruciate reconstruction may be done at the same time or later. Exact timing depends on the skin, swelling and other injuries.
Will I be able to return to my job?
Most people return to desk work within a few months. Physically demanding jobs, such as construction or industrial work, often take nine to twelve months, and some patients need modified duties.
Can the ligaments be repaired instead of reconstructed?
Some corner injuries that pull off the bone can be repaired when treated early, often with added reinforcement. Torn cruciate ligaments are usually reconstructed with grafts, and late cases usually need reconstruction.
Glossary
Patients also ask
- Can I return to sport or manual work after multi-ligament knee surgery?
- How long is recovery after multi-ligament knee reconstruction?
- Is multi-ligament knee surgery done in one operation or in stages?
- What affects the cost of multi-ligament knee surgery in Qatar, and will insurance cover it?
- What are the risks of multi-ligament knee reconstruction?
Related