Conditions
LCL and Posterolateral Corner Injury Treatment in Doha
Quick answer
The posterolateral corner is a group of structures on the outer back of the knee, led by the lateral collateral ligament (LCL), that controls outward bending and rotation. Mild sprains heal with bracing, but complete tears heal poorly and are usually repaired or reconstructed early, advises Dr. Pablo Gelber, knee surgeon at Aman Hospital in Doha, Qatar.
What are the LCL and posterolateral corner?
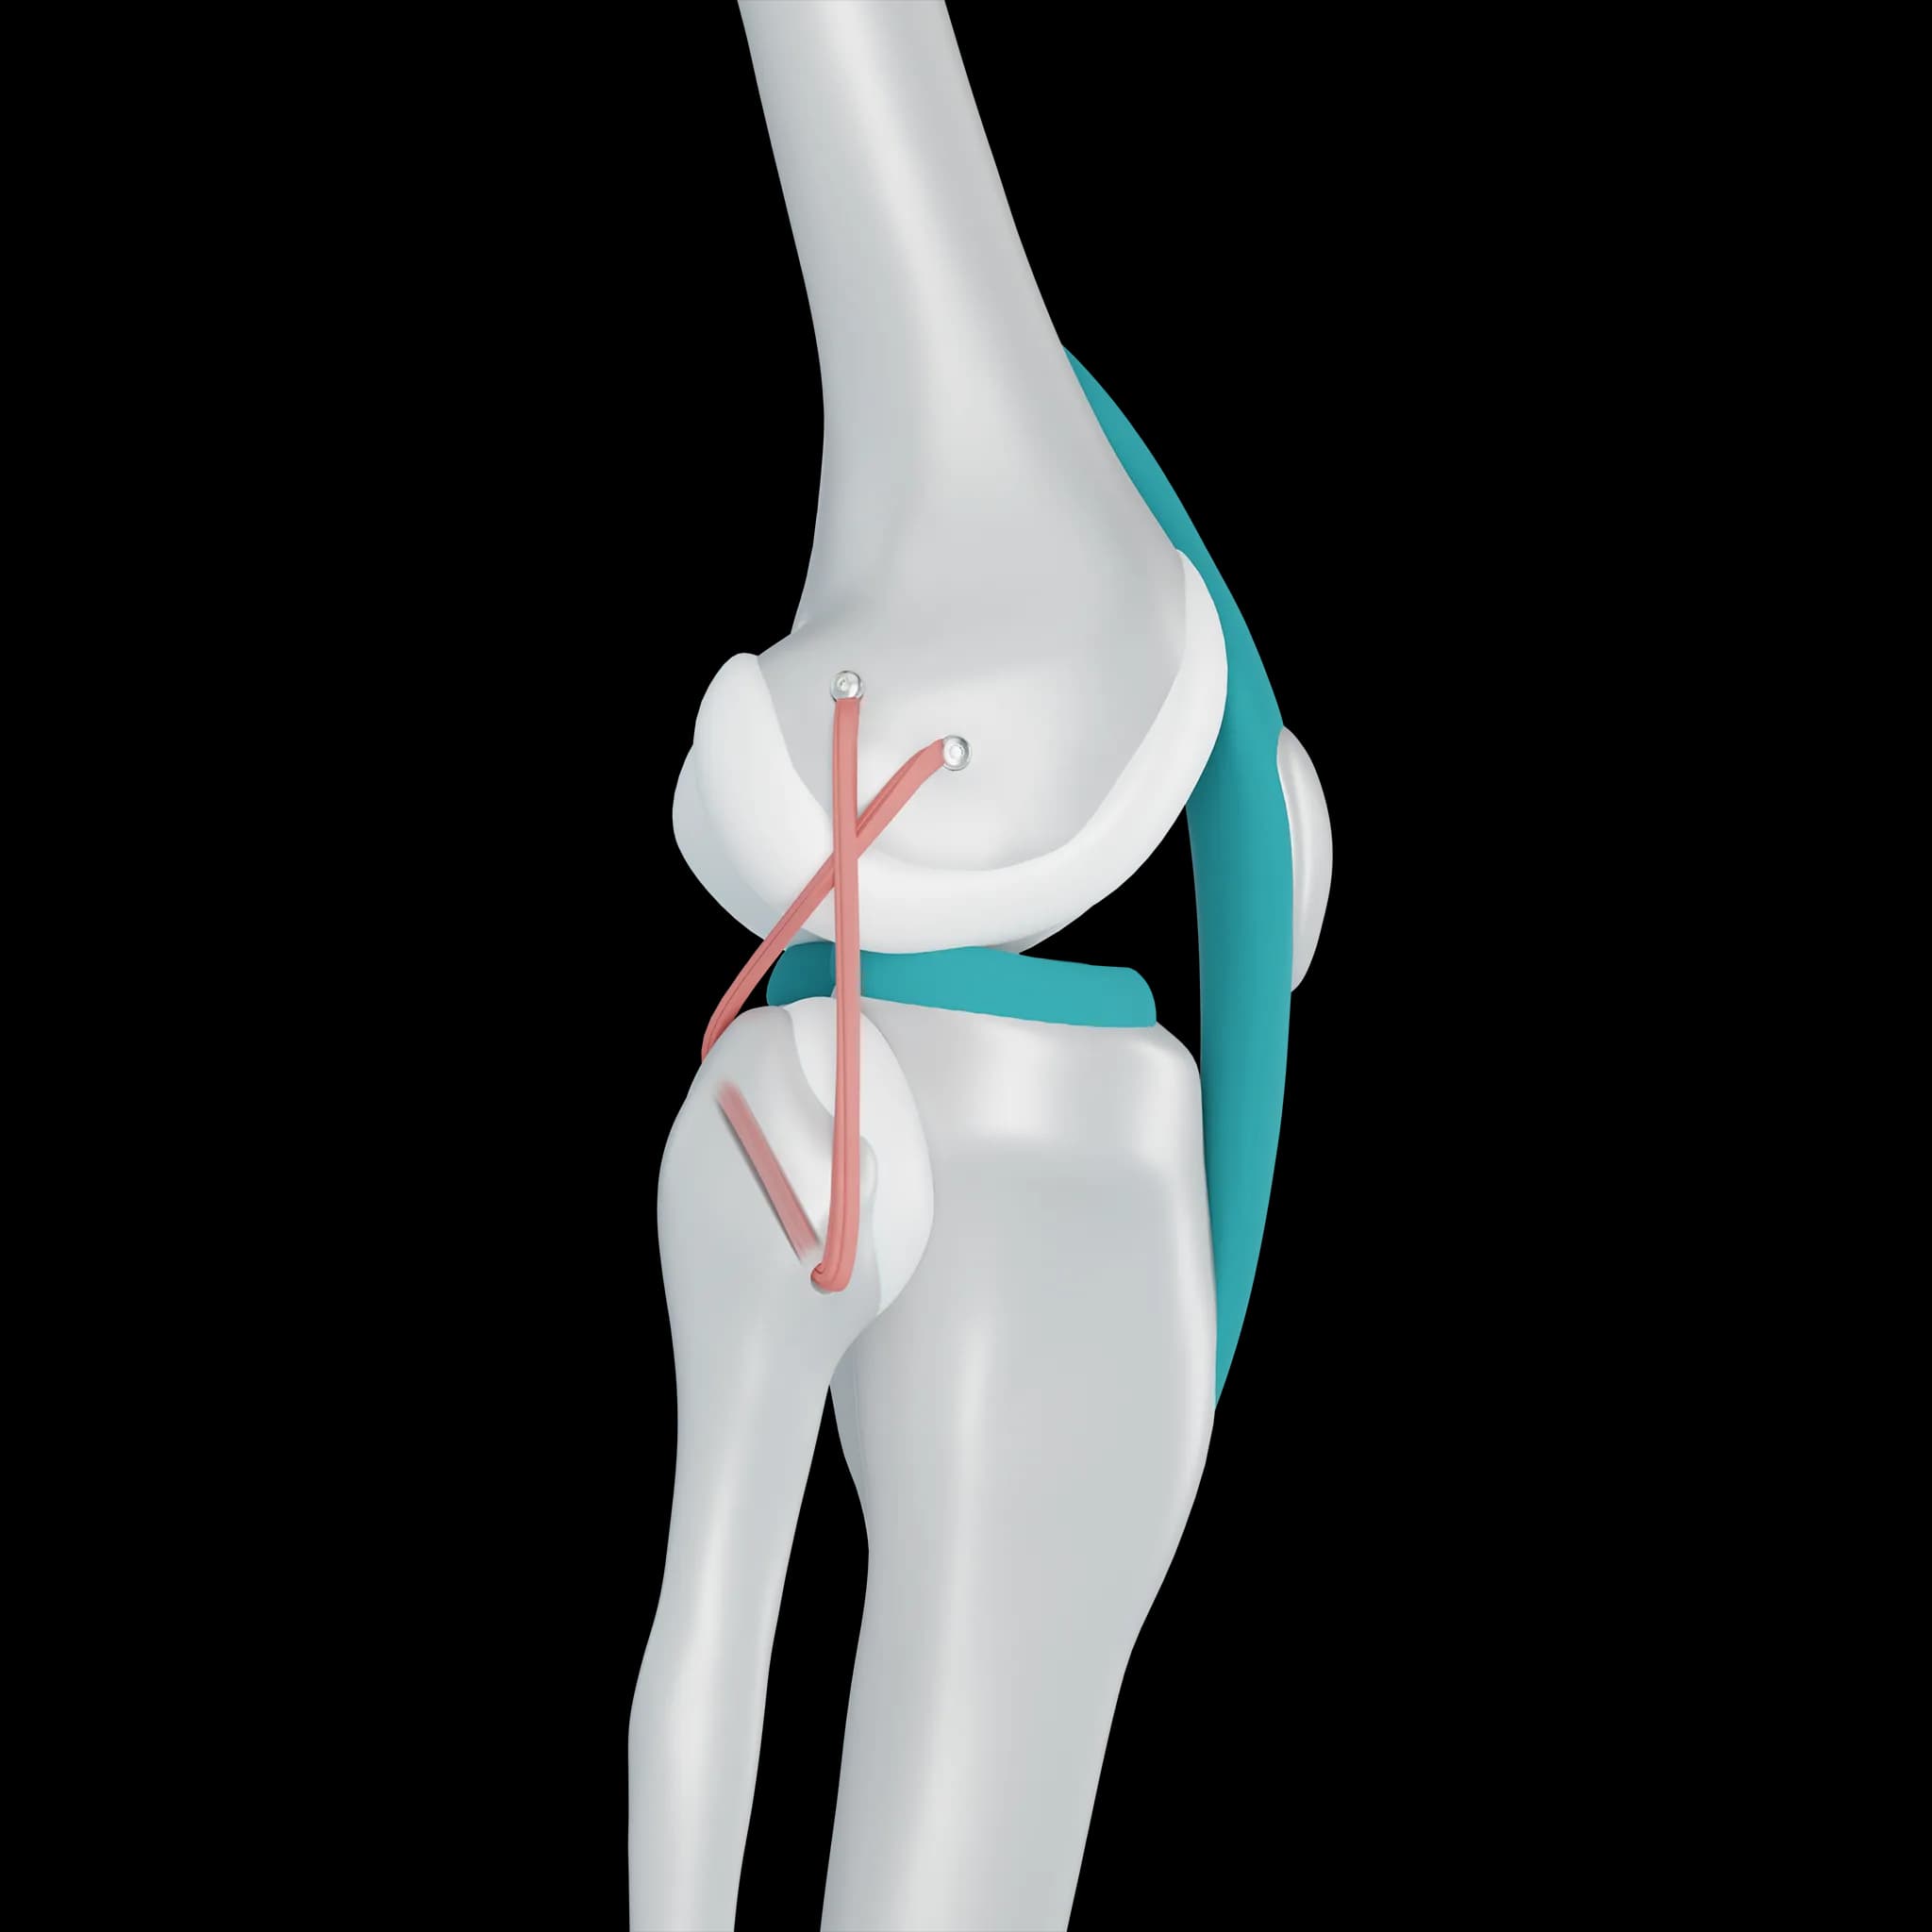
The lateral collateral ligament (LCL) is a cord-like ligament on the outer side of the knee, running from the thigh bone (femur) to the top of the fibula, the thin bone beside the shin. It stops the knee bending outwards, the bow-legged direction.
The LCL is part of a wider group called the posterolateral corner (PLC). This includes the popliteus tendon and the popliteofibular ligament, which together control outward rotation of the shin. These structures work with the cruciate ligaments, so PLC injuries often occur alongside ACL or PCL tears.
Why these injuries need early attention
Unlike the MCL on the inner side, the outer structures of the knee heal poorly on their own when completely torn. If a significant PLC injury is missed, the knee can remain loose and twisting, and an ACL or PCL reconstruction done at the same time is more likely to stretch or fail.
Complete PLC tears are often repaired or reconstructed within the first few weeks, while the anatomy is still clear. Later surgery is still possible, but usually requires reconstruction rather than repair.
Symptoms, in patients' own words
- "It hurts on the outside of my knee" or at the outer back of the knee
- Swelling and bruising on the outer side
- "My knee feels like it bends backwards or outwards when I stand"
- Instability on stairs or when turning, especially away from the injured side
- A thrust or wobble of the knee when walking, in more severe injuries
- Numbness, tingling or weakness lifting the foot, which can mean the peroneal nerve near the fibula has been injured
Weakness lifting the foot, foot drop, or a cold, pale foot after a knee injury needs urgent emergency assessment.
Causes and who gets it
PLC injuries are usually caused by a blow to the inner front of the knee that pushes it outwards and backwards, or by a hyperextension injury where the knee is forced past straight. Contact sports such as football and rugby, falls from height, motorbike accidents and road traffic collisions are typical causes.
In Qatar, high-speed collisions and desert sports such as dune bashing and quad biking account for many of the more severe cases. Isolated LCL sprains are seen in football, martial arts and wrestling.
Diagnosis
Examination is central. Dr. Gelber tests outward stress (varus) at different degrees of bend, the dial test that compares shin rotation on both sides, and checks the ACL and PCL. He looks at how the patient stands and walks, and checks foot sensation and strength for nerve involvement.
An MRI scan shows which structures are torn and where. Stress X-rays may be used to measure the opening on the outer side. X-rays also detect a fracture of the top of the fibula, which can mean the LCL has pulled off with a fragment of bone. Standing long-leg X-rays are useful in chronic cases, because bow legs place extra strain on any reconstruction.
Treatment
Isolated grade I and II LCL sprains are usually treated with a hinged brace, early protected movement and physiotherapy, and often heal within several weeks.
Complete LCL tears and significant PLC injuries are usually treated surgically:
- Repair, when the structures have pulled off the bone and are seen early
- Reconstruction with a tendon graft, which recreates the LCL and the other PLC structures
- Reconstruction of any torn ACL or PCL at the same operation, so the whole knee is balanced
- In chronic cases with bow legs, an osteotomy to correct alignment may be considered before or with the ligament surgery
After surgery, the knee is protected in a brace, with partial weight bearing for several weeks.
Recovery and when to see a specialist in Doha
Isolated sprains often allow a return to sport within two to three months. After PLC reconstruction, return to running is usually around six months, and to contact or pivoting sport around nine to twelve months, guided by strength and stability testing.
See a knee specialist promptly if the outside of the knee is painful and unstable after a fall or collision, if the knee bends backwards when you stand, or if you have numbness in the foot. Dr. Gelber assesses outer knee ligament injuries at Aman Hospital in Doha and plans treatment early, while the widest range of options is still available.
Frequently asked questions
Can an LCL tear heal without surgery?
Partial tears usually heal with a brace and physiotherapy. Complete LCL tears, and tears involving the wider posterolateral corner, heal poorly on their own and are usually treated with repair or reconstruction.
Why did my ACL reconstruction stretch out?
One recognised reason is an untreated posterolateral corner injury, which puts extra strain on the graft. When an ACL graft fails, the outer side of the knee and leg alignment are examined carefully before revision.
What does numbness in my foot after a knee injury mean?
The peroneal nerve runs around the top of the fibula and can be stretched in outer knee injuries. Numbness or weakness lifting the foot needs prompt assessment, and a cold or pale foot is an emergency.
How soon should a posterolateral corner injury be operated on?
Where surgery is needed, it is often done within the first two to three weeks, once the skin and swelling allow. The exact timing depends on the other injuries and on the patient's overall condition.
Glossary
Patients also ask
- Can an untreated posterolateral corner injury make ACL surgery fail?
- Does an LCL or posterolateral corner injury need surgery?
- My knee bent outward in a fall and now the outside hurts. What could it be?
- Why is my foot numb or weak after an injury to the outside of my knee?
- What is the posterolateral corner of the knee?
- Why are posterolateral corner injuries often missed, and how are they diagnosed?
Related