Patient question
My surgeon says I need my shinbone cut to fix my kneecap. Why?
 Dr. Pablo GelberOrthopaedic Knee Surgeon
Quick answer
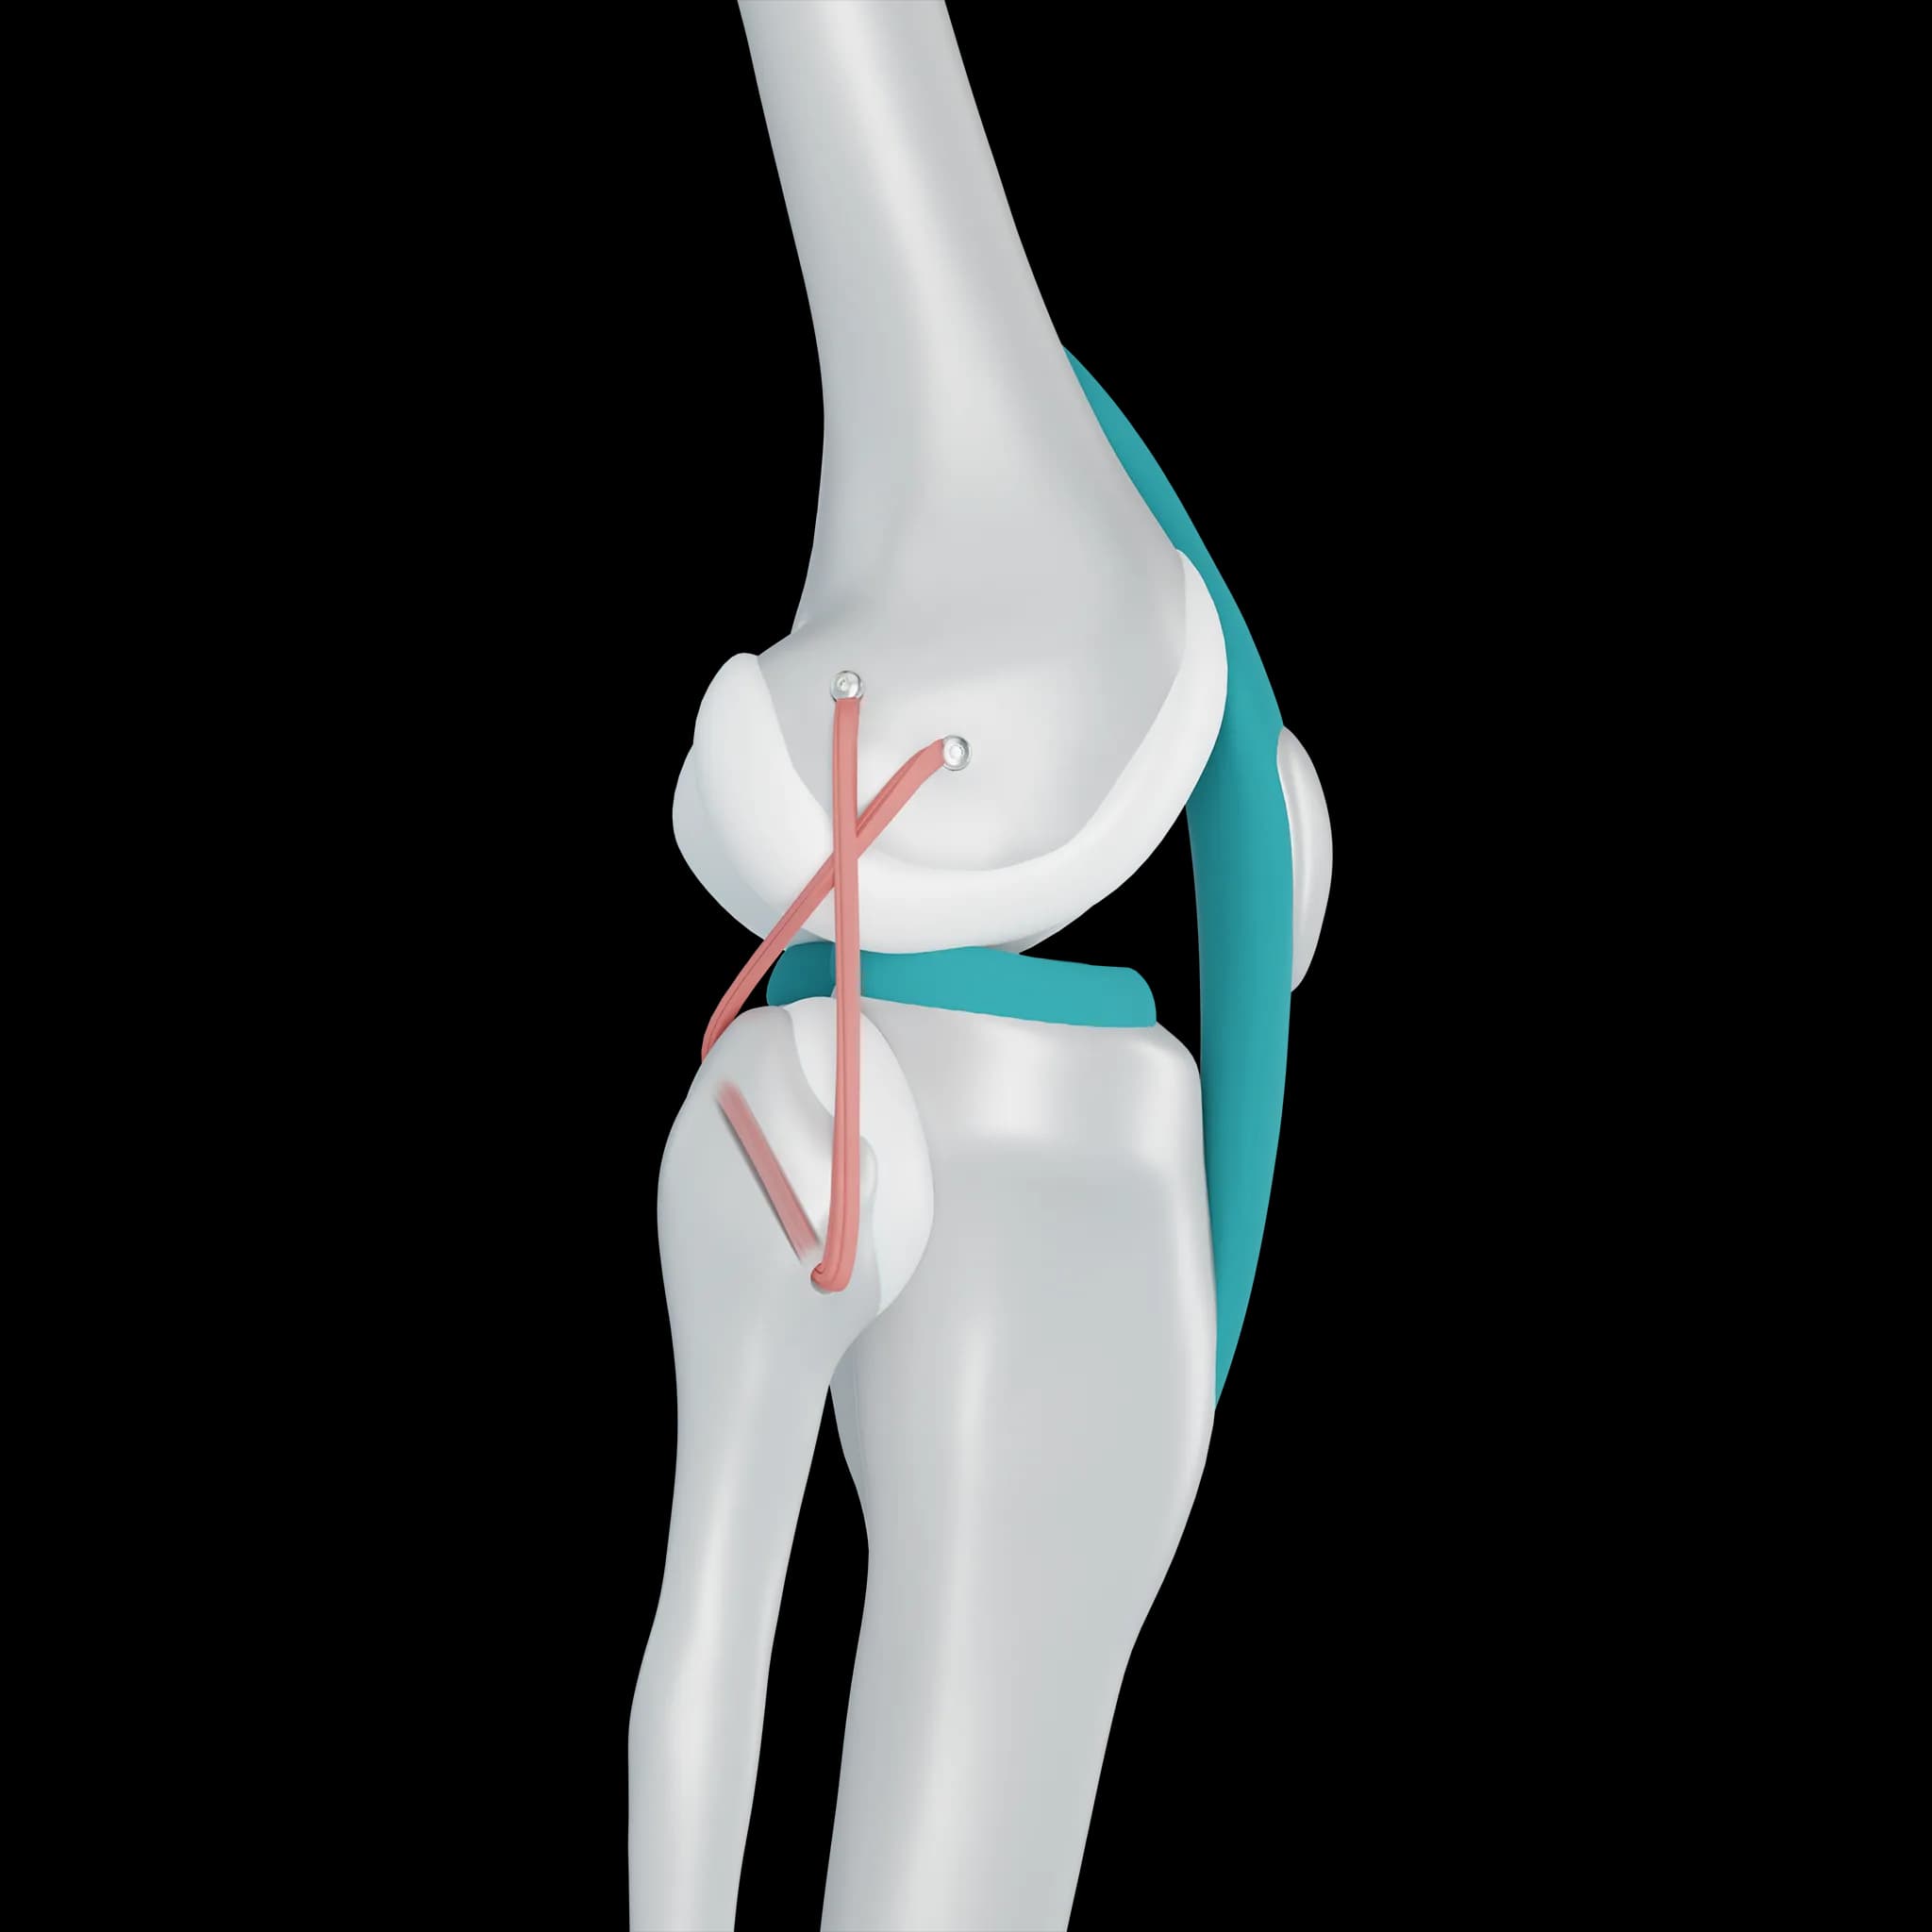
The bone is cut because the problem is often in the alignment, not just the ligaments. If the kneecap tendon attaches too far outward or the kneecap sits too high, moving that attachment corrects the pull at its source, explains Dr. Pablo Gelber, knee surgeon at Aman Hospital in Doha.
Ligaments hold, bones steer
The MPFL is the main ligament stopping the kneecap from sliding outward, and reconstructing it is a common operation. But if the bones keep steering the kneecap off track, a new ligament alone may be overloaded and stretch or fail.
A tibial tubercle osteotomy changes the steering. It is often added to an MPFL reconstruction when the scans show a clear alignment problem.
The measurements your surgeon may mention
- TT-TG distance: how far outward the tendon attachment sits relative to the groove of the thigh bone, measured on CT or MRI
- Patellar height: whether the kneecap rides high, measured on X-ray or MRI
- Trochlear shape: how shallow or flat the groove is
- Cartilage condition: whether certain parts of the kneecap are worn
No single number decides surgery. They are combined with how often the kneecap dislocates and how much it limits you.
Questions worth asking
Ask which measurement is abnormal in your knee, what would happen with ligament surgery alone, how long you will be on crutches and what restrictions apply to work, driving and prayer positions. It is reasonable to ask for time to think, or to seek a second opinion, before agreeing to a bone operation.
When this is not the answer
Kneecap pain without instability and without a clear alignment problem usually responds to physiotherapy focused on hip and thigh strength. At Aman Hospital, Dr. Gelber explains when an osteotomy is likely to help and when it is unlikely to change your symptoms.
Frequently asked questions
Will my kneecap still dislocate after this surgery?
The aim is to make further dislocations much less likely, and in many patients it does. No operation removes the risk entirely, and rehabilitation still matters.
Can both knees be done at the same time?
This is rarely advised, because each leg needs protected weight-bearing for several weeks. Usually the more troublesome knee is treated first.
Related