Patient question
Why does my kneecap keep dislocating?
 Dr. Pablo GelberOrthopaedic Knee Surgeon
Quick answer
Recurrent kneecap dislocation usually comes from a combination of a torn inner restraining ligament and the knee's own shape, such as a shallow groove, a high-riding kneecap or an outward-pulling tendon. Finding which factors are present is what guides treatment, says Doha knee surgeon Dr. Pablo Gelber of Aman Hospital.
The kneecap's three lines of defence
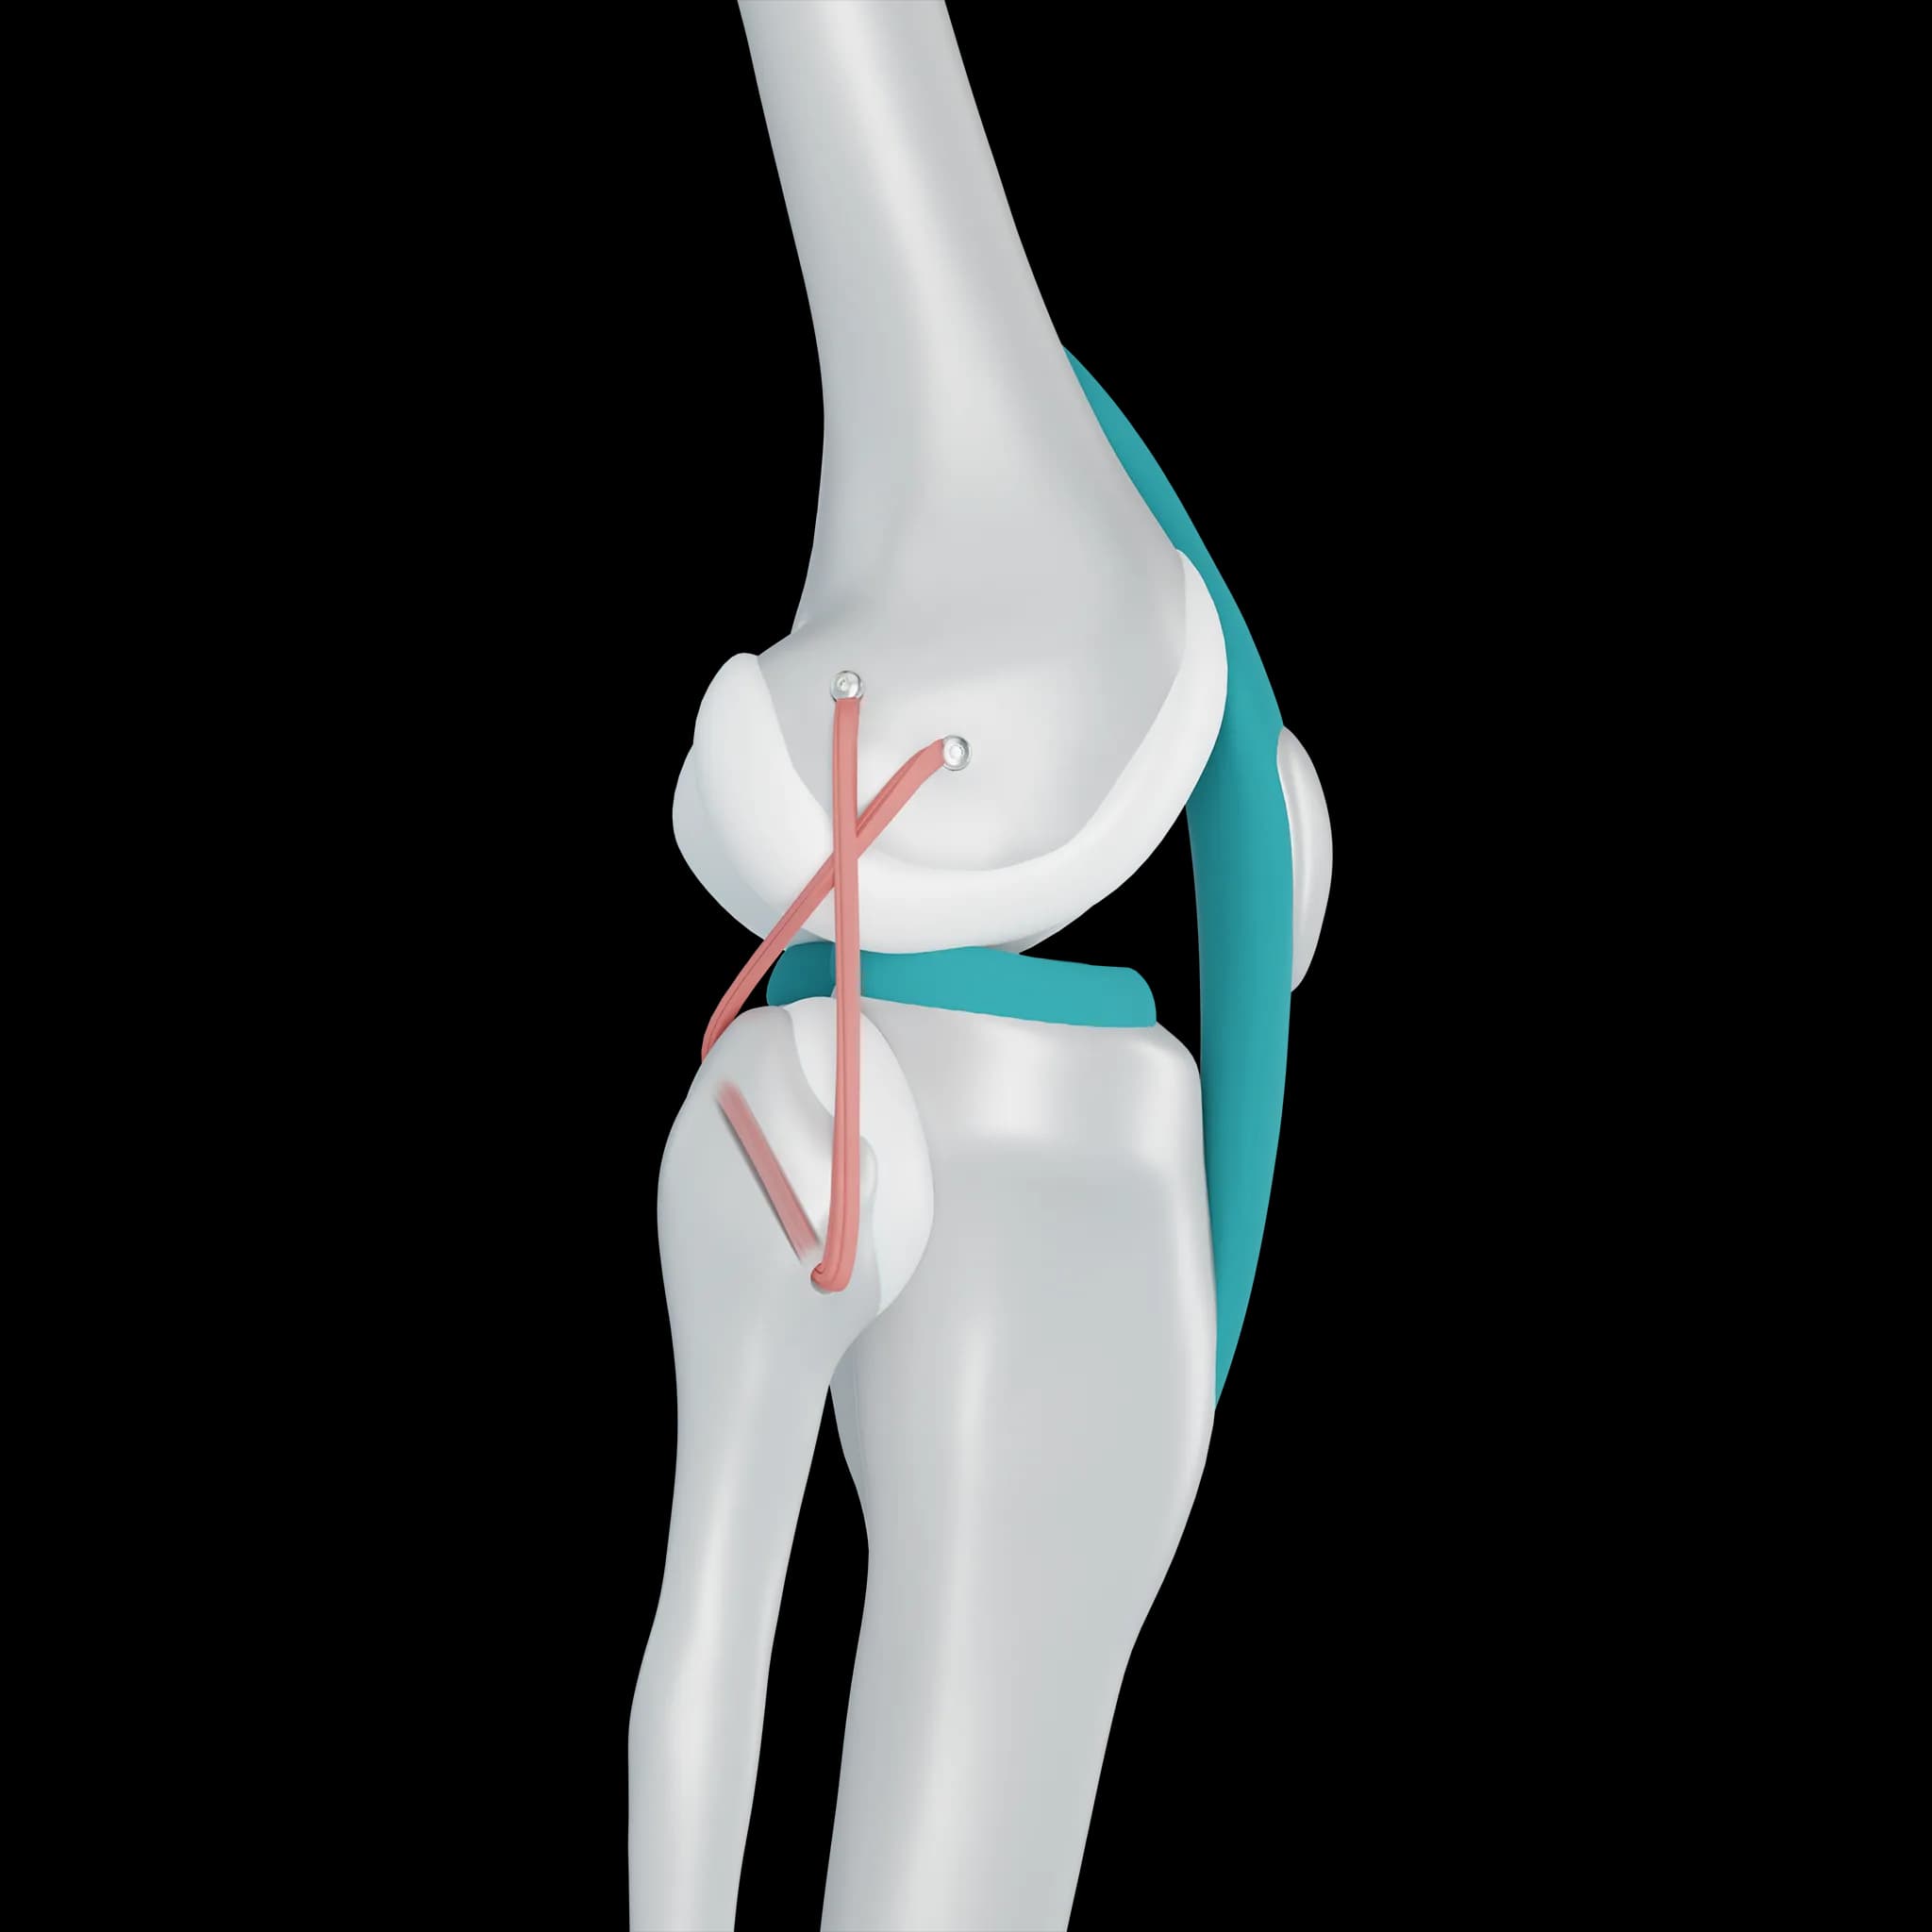
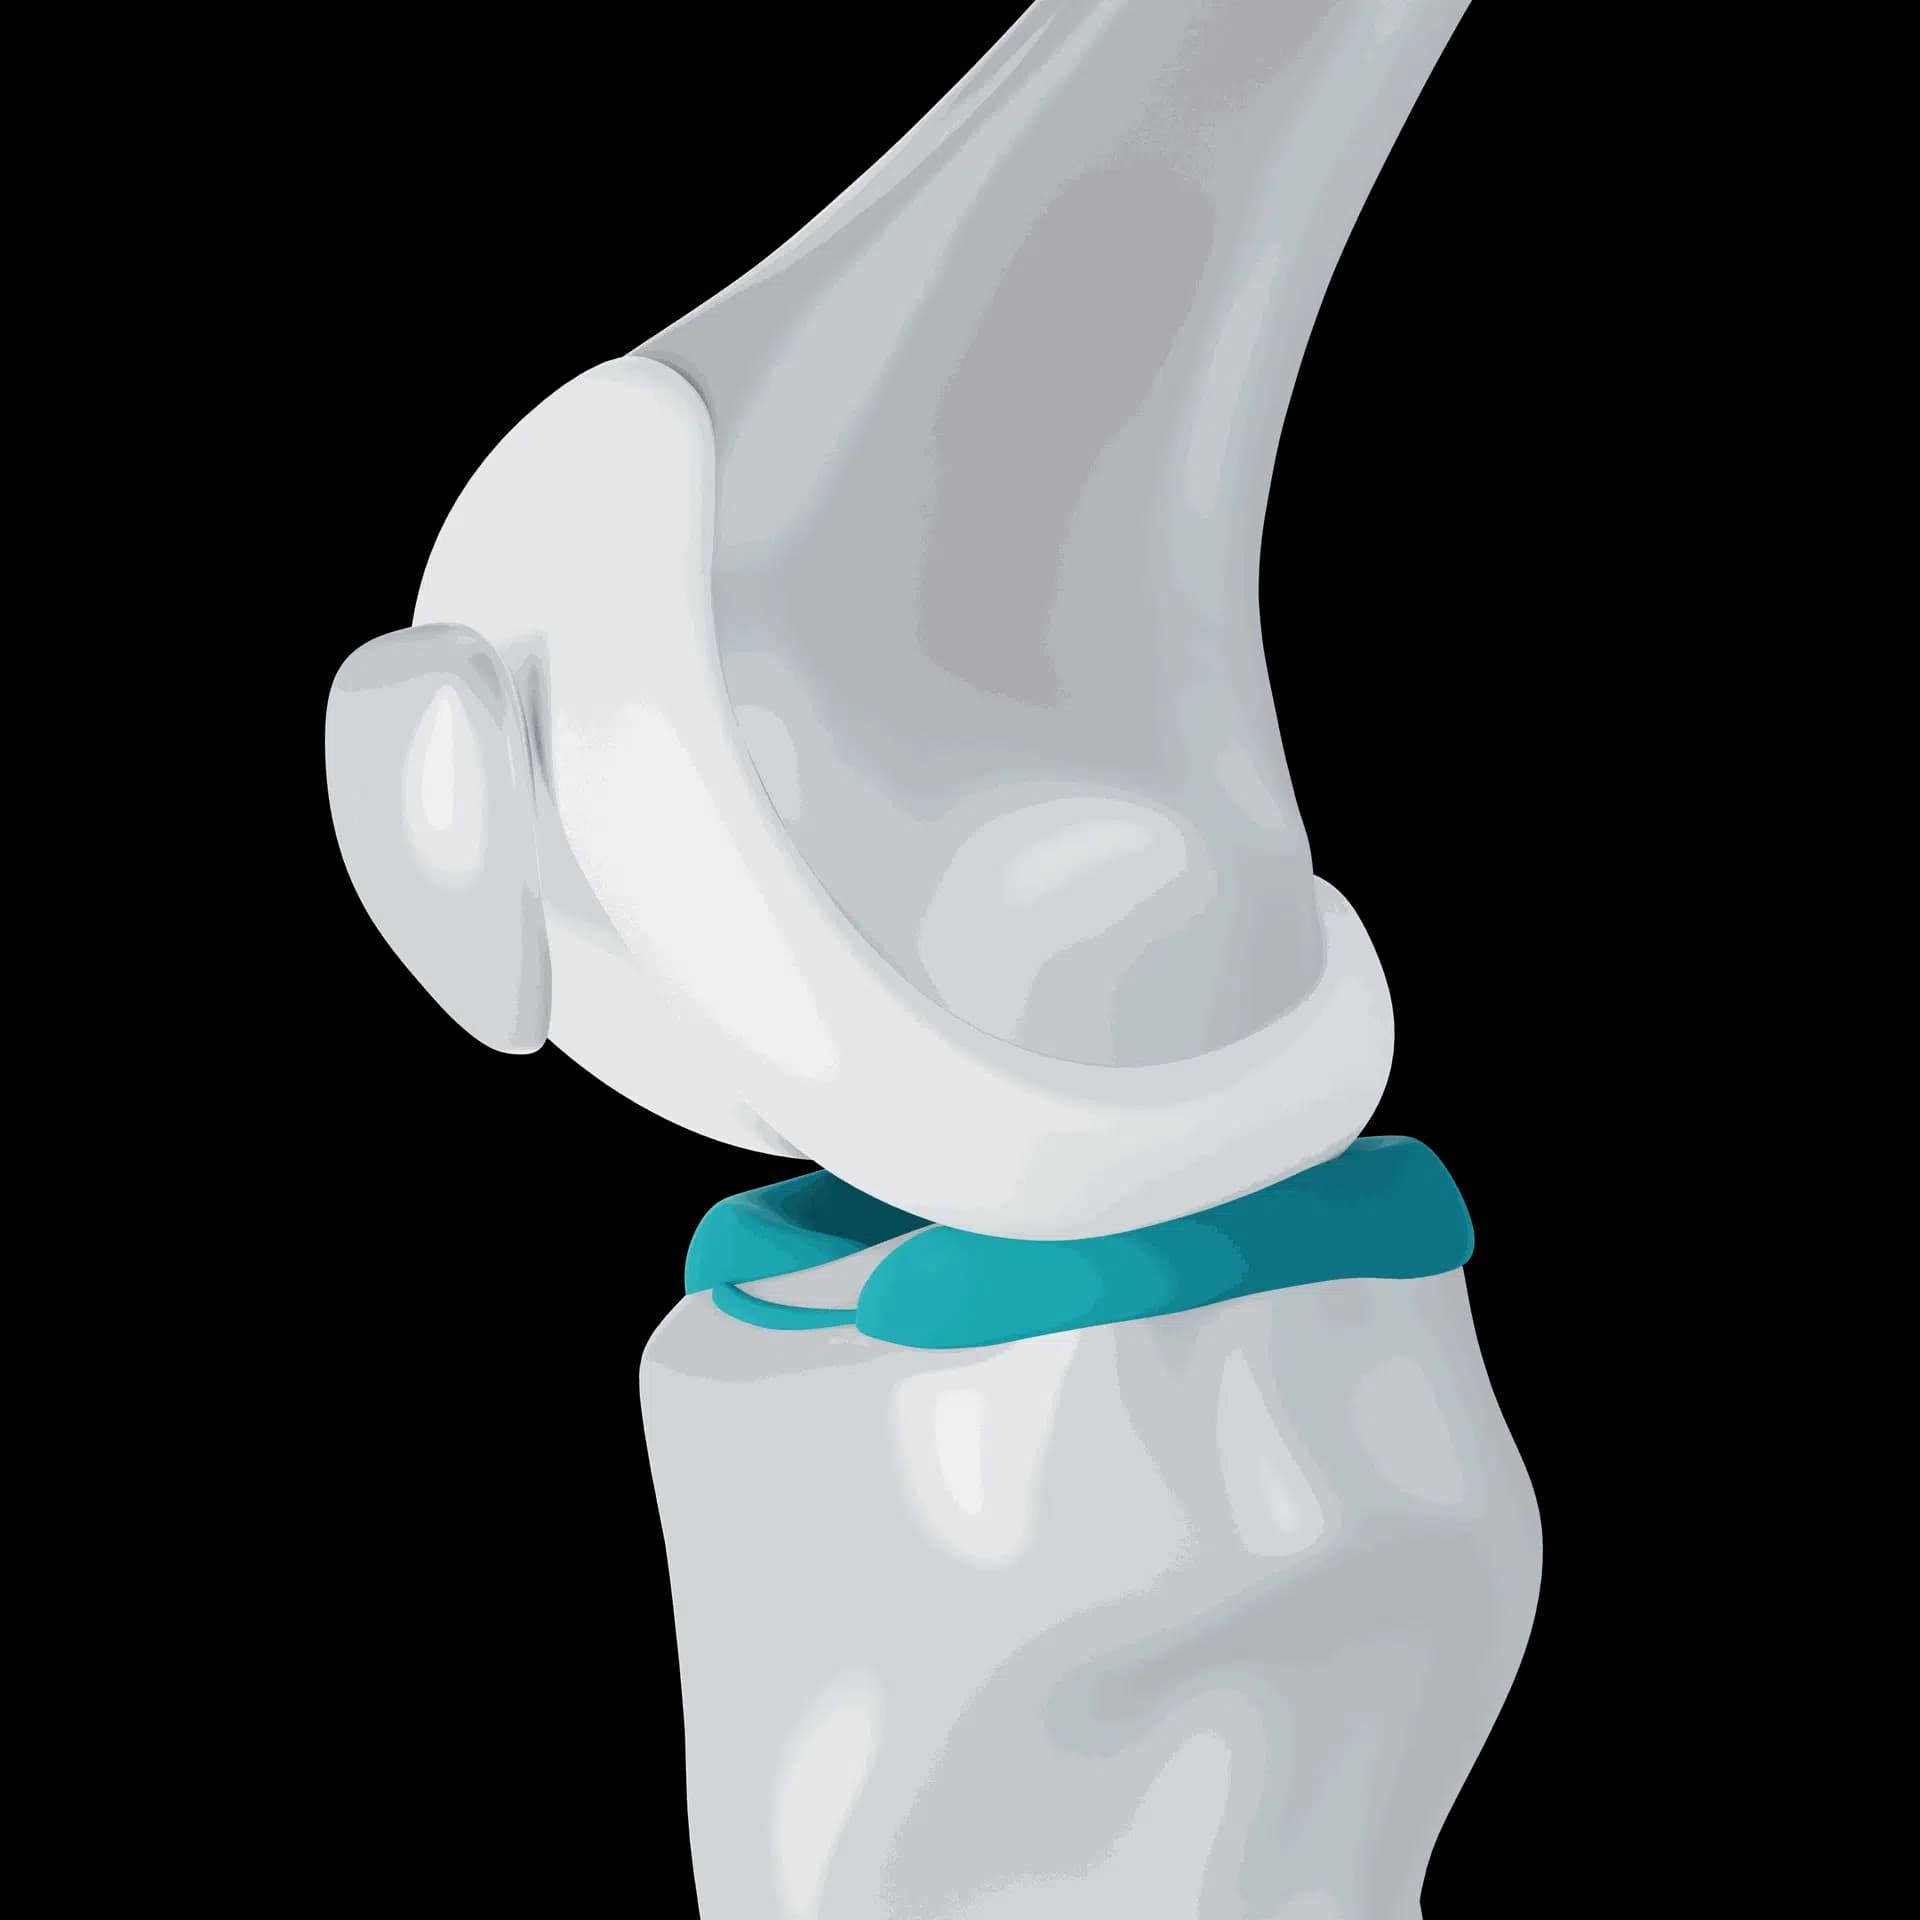
A kneecap stays on track thanks to three things working together. The bony groove (trochlea) at the end of the thigh bone acts like a rail. The soft tissues, above all the medial patellofemoral ligament (MPFL), act like a tether on the inner side. And the muscles, especially the quadriceps and hip muscles, steer it dynamically.
When one of these is weak the others can often compensate. When two or more are deficient, the kneecap can slip out with surprisingly little force, sometimes just turning in the kitchen or stepping off a pavement.
The common anatomical causes
- Trochlear dysplasia: the groove is shallow, flat or even bumped, so the rail does not hold the kneecap
- Patella alta: the kneecap sits higher than usual and only enters the groove late in bending, leaving it unprotected in the first part of movement
- Lateralised tendon attachment: the patellar tendon inserts too far to the outer side of the shin, pulling the kneecap outwards
- Rotational alignment of the thigh or shin bones, or knock knees
- A stretched or torn MPFL that never healed tight after the first episode
- Generalised ligament laxity
How the cause is identified
Examination looks at how the kneecap moves as you bend, how far it can be pushed sideways, whether this makes you apprehensive, and your overall leg alignment and flexibility. MRI shows the ligament, the cartilage and the groove shape, and allows measurements of kneecap height and tendon position. A CT scan is sometimes used to measure bone rotation in more detail.
Why the cause decides the treatment
If the main problem is the torn ligament with reasonably normal bones, strengthening or MPFL reconstruction may be enough. If the kneecap rides high or the tendon pulls strongly outwards, a tibial tubercle osteotomy may be added. A severely flat groove sometimes needs a trochleoplasty. At Aman Hospital in Doha, Dr. Gelber tailors the plan to the factors found in each patient rather than using one operation for everyone.
Frequently asked questions
Is this something I was born with?
The shape of the groove and the height of the kneecap are largely developmental, and they can run in families. The ligament tear, by contrast, is the result of the dislocations themselves.
Can exercises fix a shallow groove?
Exercises cannot change bone shape, but stronger, better-coordinated muscles can improve control of the kneecap and are helpful for many patients even when the anatomy is not ideal.
Related